|
|
json version - view hidden posts
View article without comments
by C L Hallmark
Sunday, Dec. 26, 2004 at 3:08 AM
George W. Bush apparently is wearing a medical device for "persons at risk of cardiac arrest." It is a LifeVest wearable defibrillator. He started using it sometime after his January 2002 fainting spell, which was attributed to choking. Based on photos showing him wearing the device, one can conclude the fainting was due to atrial fibrillation (AF), which his father also had.
lifevest_duo_back_2.jpg, image/jpeg, 548x236
PHOTOS Show George W. Bush Seriously Ill Physically
His father's AF was caused by Graves' hyperthyroidism, which Barbara Bush also has. Bush Jr likely has AF and, less likely, Graves', based on his family history and symptoms. The AF may have caused a stroke or TIA (mini-stroke), of which physicians watching the debates detected symptoms. Observers have noted psychological symptoms consistent with this and with Wernicke-Korsakoff disease. NOTE: If the photos have not uploaded to this site, see also: http://colombia.indymedia.org/news/2004/12/20372.php.
[December 22, 2004] "The President remains in supurb physical condition," said Adam M. Robinson, Jr., commander of the National Naval Medical Center in Bethesda, MD, after the president's fourth annual physical at the center on December 11.
"The doctors said that Mr. Bush had a 'low' to 'very low' risk of coronary artery disease, although they found evidence of minimal calcification of the coronary arteries themselves. As a preventative, they recommended that Mr. Bush take a daily aspirin and a statin, or cholesterol-lowering drug," reported the New York Times.
It's interesting that his doctors advised him to take aspirin and statin. Aspirin is used to prevent clotting, which is a problem with AF (the condition he apparently wears the LifeVest for). Statins are the most potent cholesterol-lowering agents, lowering LDL (so-called "bad cholesterol) by 30-50 percent. They are less effective than fibrates in lowering triglycerides and raising HDL ("good cholesterol"). But Bush's doctors said he had a "low" to "very low" risk of heart disease, and his total cholesterol level was listed as 170 mg/dL, which is considered within the normal range.
There is ongoing research into other areas where statins appear to have an effect, including dementia. Science Daily recently reported (11/17/04): "The cholesterol-lowering drug atorvastatin slowed down mental decline and improved depressive symptoms in people with Alzheimer’s disease"
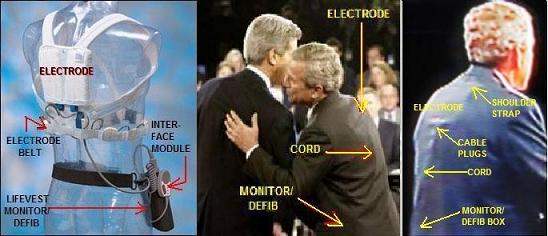
In contrast to the "fit for duty" report, the photos below show Mr. Bush at a presidential debate, with parts of a LifeVest wearable defibrillator clearly visible underneath his suit jacket.
#file_1#
The LifeVest (left) has an electrode belt with four sensing/ECG electrodes. These send signals to the heart monitor/defibrillator, typically worn like a holster. When the monitor detects a life-threatening heart arrhythmia, it sends a signal to the small, handheld patient-interface module (a little like a computer "mouse" but with just buttons and alarms). The module provides an audible alarm. The user, if able to do so, depresses two buttons on the module to hold off a shock from the defibrillator. If the user faints and is unable to press the buttons, the defibrillator sends an electrical pulse to the large shocking electrode on the patient's back and a smaller one on the chest. The pulse can be repeated until the heart starts pumping blood effectively, up to five pulses.
In the center photo, showing Mr. Bush and Sen. Kerry at a debate, one can clearly see the shocking electrode between the shoulder blades as well as the electrical cord leading down to the monitor/defibrillator. (As for the small square patch near Mr. Bush's ear in this photo, I do not know. It is some kind of patch -- not a video artifact.)
The photo on the right, from another debate, gives another view of the LifeVest components.
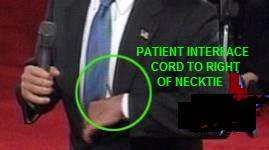
Below we see the president adjusting his necktie, and as he does so, revealing a gray cord like that on the interface module ("mouse"), leading down to the monitor/defibrillator. The interface module possibly was located behind his tie.
#file_2#
This news could turn out to be the story of the year -- for 2005 -- if reporters ask the right questions to the right people.
Some time between the fainting (pretzel) incident of January 2002 and the following summer, the president apparently began wearing the device. The photo of Mr. Bush at his ranch was taken on August 9, 2002.
#file_3#
THE FAINTING INCIDENT OF JANUARY 2002
On January 13, 2002, President Bush lost consciousness while sitting on a couch in the White House, watching a football game. His head hit the floor, resulting in an abrasion on his left cheekbone and a small bruise on his lower lip. The incident was blamed on a combination of (a) Mr. Bush not feeling well in previous days and (b) an improperly eaten pretzel. Their combined effect was to slow the president's heart. The description suggests a vasovagal attack: A pretzel lodged in his throat stimulated the vagus nerve to send a signal to his heart, slowing it down and reducing blood flow so much he fainted, according to White House physician Col. Richard J. Tubb, M.D.
#file_4#
Of course, even in this day of telemedicine, it is difficult and uncertain for anyone to diagnose a patient without having access to examination and test records. That doesn't stop physicians and psychologists from trying, especially on someone with President Bush's visibility. Obviously, considerable testing and examination have been done; but the American public does not always have the latest results, as they found out after other presidents, including Roosevelt and Kennedy, left office. Besides photographic evidence, there are observations and quotes from doctors, based on hours of Bush TV appearances, voluminous reports in the media, and the president's own words.
ATRIAL FIBRILLATION (AF)
In the January 2002 pretzel-choking episode, according to President Bush, the period of unconsciousness was brief -- a few seconds. When fainting begins and ends suddenly, the cause of fainting usually is not what his doctors reported (vasovagal syncope) but instead is an abnormal heart rhythm such as atrial fibrillation (AF). Chronic AF is consistent with Mr. Bush's requirement for constant monitoring and immediate access to defibrillation. Atrial fibrillation can lead to disastrous consequences if the patient is capable of sustaining a very rapid preexcited ventricular response with conduction over the accessory pathway. The rapid heart rate can produce syncope (fainting); or, more important, AF may cause ventricular fibrillation and sudden cardiac death. The LifeVest the president wears terminates ventricular fibrillation or ventricular tachycardia (overspeed) to prevent sudden cardiac death. This may be the reason the president wore the device during the debates, even though he risked exposing his vulnerability, especially if the device alarm sounded.
According to the Framingham Offspring study of AF, a person whose parent had AF is 50 percent more likely to have it than the general population. President Bush's father had it during his presidency. While jogging at Camp David on a Saturday afternoon (May 4, 1991), Bush Sr developed shortness of breath, chest tightness, and a general feeling of fatigue. A White House physician discovered Bush had a rapid irregular heartbeat, ultimately diagnosed as atrial fibrillation caused by Graves' disease, a form of hyperthyroidism (overactive thyroid).
Vagal-mediated AF is a well described phenomenon and often occurs in older athletes, which our current president, George W. Bush, is. As far as treatment, there are many different drug options. Blood thinners are often prescribed to reduce the risk of blood clots. President Bush's latest medical report (December 2004) included advice to take aspirin, which is a well known anti-clotting agent. Clotting can lead to strokes, discussed later.
Although atrial fibrillation usually is controllable with treatment, it may become a lasting, chronic, condition. In the president's case, it apparently has, as his physicians evidently have decided to have him wear an external device that can continuously monitor his heart and shock it back into effective operation in case of an attack.
Hyperthyroidism, hypertension, and other diseases can cause arrhythmias, as can recent heavy alcohol use (binge drinking). Some cases have no identifiable cause. The president says that he stopped drinking when he was 40, so binge drinking is not an issue. However, both of his parents have the Graves' disease form of hyperthyroidism and it is hereditary and must be considered.
The earliest photo I have seen of President Bush wearing the LifeVest was the one taken in August 2002. He probably started wearing the LifeVest between the January 2002 pretzel incident and this. The most likely time would seem to be after his June 28, 2002 colonoscopy, for which he was put under anesthesia at Camp David, MD -- that is, some time in July 2002.
At any rate, the president bears watching for symptoms of AF, which include: heart palpitations (sensation of rapid heartbeat), irregular pulse, shortness of breath (especially during physical activity or emotional stress), chest pain (angina), weakness and fatigue, dizziness and confusion, lightheadness, or confusion. If the condition remains untreated, serious complications may occur, including stroke, heart attack, and heart failure.
EVIDENCE OF STROKE OR TIA
The evidence of atrial fibrillation is strong, based on photographic evidence that Mr. Bush wears an anti-arrythmic device, his father's having it, a confirmed sudden-fainting spell, numerous falls, and observation-at-a-distance. The evidence of a stroke or TIA is less strong. It is symptomatic and based observation-at-a-distance -- TV appearances and news reports -- but it is there.
A stroke or TIA (transient ischemic attack) is one possible consequence of AF itself. A TIA basically is a mini-stroke.
Many observers, including physicians, have been concerned or even alarmed at the symptoms President Bush has evidenced in TV appearances.
The photo below shows the drooping mouth noticed by Dr. W. Kendall Tongier, M.D. of Dallas, Texas.
#file_5#
After watching the third presidential debate, Dr. Tongier posted on the Dallas Morning News website about his concerns that the president may have had a stroke. Dr. Tongier has been an anesthesiologist for 15 years. His post said:
"Having watched the first two debates from start to finish, I was looking forward to listening to a spirited debate between Bush and Kerry. Unfortunately, I barely heard a word that was said. Instead, I found myself staring at and concentrating on the president's drooping mouth."
"As a physician and a professor, I tend to pick up on signs and symptoms of physical problems better than most other people. I am highly concerned with what I saw. The drooping left side of the President's face, his mouth and nasolabial fold (the crease in the face running from the nostril to the side of mouth) may be indicative of a recent stroke, TIA (transient ischemic attack) or, possibly botox injections. I sincerely hope this was nothing more than botox injections. The other options are truly scary given an upcoming election for president in three weeks."
In a phone interview reported by Salon.com, Dr. Tongier stressed that he's not a neurologist, and no doctor can make a diagnosis from a 90-minute debate. But he did explain why he found Bush's face so distracting on TV: "It struck me across the face to the point where I wasn't really listening to the debate. It looked like the left side of his mouth was downturned. You know how he sneers at times. At first I thought that's what it was, but it didn't change when his face was at rest. It changed when he talked, but you'd expect that. It's the loss of muscle tone there that's really kind of concerning. And it was pretty much persistent throughout the entire debate."
"It certainly could be something as benign as an overzealous botox injection, which causes the paralysis, which is essentially how botox works. A lot of people will get them around the nasolabial fold to decrease those lines. If it's botox, it can be a short-term reaction after an injection. It could last for 24 hours and be gone. But I'd like to see the Bush campaign at least give an explanation."
Not only was there no explanation, but the president delayed his annual medical examination until after the election. Even now, as far as I know, the complete details, including tests made and the metrics of those tests, have not come out -- only a conclusion that he is in "supurb condition." If the speculation is true, the writers of the president's medical report should be held to account for the discrepancies.
Atrial fibrillation is an irregular heartbeat in which the upper chamber of the heart quivers rapidly rather than beats. Even if it does not result in life-threatening ventricular fibrillation, the quivering motion is not forceful enough to send all the blood to the heart's lower chambers (ventricles), and the blood pools, thus allowing clots to develop. The clots can migrate elsewhere, including the neck or brain (in cerebral embolism), and they can cause strokes.
A series of strokes can cause a progressive impairment of brain function known as "multi-infarct dementia."
DEMENTIA
The term "dementia" refers to a group of symptoms involving progressive impairment of all aspects of brain function. Disorders that cause dementia include conditions that impair the vascular (blood vessels) or neurologic (nerve) structures of the brain. Multi-infarct dementia results from the damage caused by strokes, and there is evidence that Mr. Bush has suffered multiple small strokes or TIAs.
One other type of dementia is caused by Wernicke encephalopathy, which is bleeding and swelling of the brain due to multiple brain lesions, caused by lack of thiamine vitamin. The disease often is connected to alcoholism. Mr. Bush drank, often heavily, according many published reports, from about age 20 to age 40. He said himself one time that he couldn't remember a day he didn't have a drink.
A minority of causes of dementia are treatable. Wernicke can be treated with thiamine. If untreated long enough, the disease progresses to Korsakoff's disease, which like most of the disorders associated with dementia are progressive, irreversible, degenerative conditions.
The two major degenerative causes of dementia are (1) Alzheimer's disease, which is a progressive loss of nerve cells without a known cause or cure, and (2) vascular dementia, which is loss of brain function due to a series of small strokes. Vascular dementia may or may not play a role in the progression of Alzheimer's disease: the conditions often occur together and neither can be diagnosed definitively except until autopsy. In those with the genetic and environmental susceptibility to develop Alzheimer's disease, the concomitant presence of small infarcts (lacunar strokes) speeds up the onset of Alzheimer's disease to an earlier age than if it were to occur alone (i.e., without small infarcts). President Bush has been prescribed statins, which slow the progression of dementia, even though is over all cholesterol is within the normal range.
Dementia may be diagnosed when there is impairment of two or more brain functions, including language, memory, visual-spatial perception, emotional behavior or personality, and cognitive skills (such as calculation, abstract thinking, or judgment). Dementia usually appears first as forgetfulness. Other symptoms may be apparent only on neurologic examination or cognitive testing.
A well-respected psychoanalyst has written a psychological profile of the president, called "Bush on the Couch: Inside the Mind of the President" (ISBN: 0060736704).
Justin A. Frank, M.D., is a clinical professor in the Department of Psychiatry at George Washington University Medical Center. Since 1980 he has been a teaching analyst at the Washington Psychoanalytic Institute. He is past president of the Greater Washington Chapter of Physicians for Social Responsibility. Dr. Frank lives and practices psychoanalysis in Washington, D.C.
Among the problems Dr. Frank found in Mr. Bush are megalomania, characterized by a Manichaean worldview, delusions of persecution and omnipotence, and an "anal/sadistic" indifference to others’ pain. The Manichaean tradition is a defunct religion with a "good cop/bad cop" theology.
The book follows Mr. Bush from childhood to now and analyzes the drinking problem, the bellicose rhetoric, the verbal flailings and misstatements of fact, the religiosity and exercise routines, the hints of dyslexia and hyperactivity, the youthful cruelty to animals and schoolmates
Below are some of the problems associated with dementias, including vascular and alcoholic (Wernicke-Korsakoff syndrome). Some of the things in this list were observed by Dr. Frank in Mr. Bush. Other items exist further along in the progression of the disease.
- progressive loss of memory
- inability to concentrate
- decrease in problem-solving skills and judgement capability
- persistence in failed problem-solving modes, "staying the course" at all costs (perseveration)
- confusion
- hallucination, delusions
- altered sensation or perception
- impaired recognition (agnosia) of familiar objects or persons
- altered sleep patterns
- MOTOR SYSTEM IMPAIRMENT
-----gait changes
-----inappropriate movements
-----other impairments of motor system
- disorientation
- inability to generalize, learn, think abstractly, or perform calculations
- MEMORY DEFICIT
----- short term (can't remember new things)
----- long term (can't remember past) Persons with this may make up stories to cover up nothing but the memory lapse itself. (confabulation)
- IMPAIRED LANGUAGE ABILITY
----- inability to comprehend speech
----- inability to read (alexia)
----- inability to write (agraphia)
----- inability to find words (aphasiia)
----- inability to repeat a phrase
----- persistent repetition of phrases or words (Much has been made of President Bush's use of the word "fabulous.")
- PERSONALITY PROBLEMS
----- irritability
----- poor temper management
----- anxiety
----- depression
----- indecisiveness
----- self-centeredness
----- inflexibility
----- no observable mood (flat affect)
----- inappropriate mood or behavior
----- withdrawal from social interaction
----- inability to function in social or personal situations
----- lack of spontaneity
Some of the above have been noted by Dr. Frank in the Bush book. Some have been noted by other MD's and by medical laymen, including members of the press.
Evidence of motor-system impairment has been well chronicled by the media. Most of these incidents have come at times of particular stress. They include:
January 2002: While watching a football game, Mr. Bush fainted and injured his face. This was a time of stress, 2 weeks before his post-9/11 State of the Union address.
May 2003: Mr. Bush fell off a Sedgway gyroscopically balanced 2-wheel scooter. Another stress -- 2 weeks before a trip abroad to line up support for Iraq war.
August 2003: Mr. Bush dropped his dog Barney as Mrs. Bush handed him the dog at the TSTC Airport in Waco, Texas, to the horror of onlooking schoolgirls. In little over a week he would give only his second (the first was to announce the start of the war on Iraq) address to the nation defending the yellowcake/Wilson/Plame matter, the WMD deadend, and the growing insurgency in Iraq -- arguably his most important national address to date. This was a time of stress.
May 2004: Two days before one of very few and arguably the most important prime-time speech of his, in which he defended the Iraq war in the wake of Fallujah and Najaf unrest, Mr. Bush fell and injured his face again. His approval rating was 41 percent, the lowest of his presidency, at this time of stress.
June 4, 2004: Mr. Bush appeared with a scatch on his right cheek. Had he fallen again?
Additional symptoms that may be associated with this organic brain disease include swallowing problems. However, this and some of the above are also symptoms of hyperthyroidism.
HYPERTHYROIDISM (OVERACTIVE THYROID)
When one of a person's parents has hyperthyroidism, one cause of AF and the cause in his father's case, the chances are that 50 percent of their children will have it. Both of President Bush's parents have Graves' disease, increasing his chances of getting it even more.
The president's father was diagnosed with Graves' disease, a form of hyperthyroidism in 1991, within 18 months of Barbara Bush being diagnosed with the same thing. The chances of this happening to two unrelated persons in such a short time is about 1 in 3 million. Because of the remarkable coincidence, the Secret Service tested the water in the White House, at Camp David, at the Vice President's residence, and at Walker's Point (Bush's home in Maine) for lithium and iodine, two substances "known to cause thyroid problems." The lead investigator was Dr. Kenneth Burman, then a colonel in the Army medical corps (the same man whom the media is quoting about the thyroid cancer of Chief Justice Rehnquist).
Besides causing atrial fibrillation as it did in the case of Bush Sr and possibly Bush Jr, hyperthyroidism has the following symptoms:
-- Feeling of fullness in the throat
-- Enlargement of the thyroid, known as goiter
-- CHOKING ON FOODS
-- Irregularities in blood pressure and HEART RATE.
-- FAINTING OR DIZZINESS
-- SENSITIVITY TO LIGHT AND A CONTINUAL FEELING THAT THERE IS SOMETHING IN THE EYES (This could explain the president's rapid eye-blinking, noted in the presidential debates.)
The onset of Graves' frequently is during times of intense stress. Bush Sr fell ill with Graves' and AF during the first Iraq war.
The president's physicians should be looking carefully at his thyroid antibodies and conducting a complete thyroid bloodwork panel in view of his symptoms and family history. Of course, Mr. Bush should level with the American people on this.
OTHER SYMPTOMS OF HYPERTHYROIDISM
Enlarged thyroid gland
Rapid heart beat (tachycardia) or heart palpitations
ATRIAL FIBRILLATION (President Bush appears to have worn a LifeWest defibrillator since about July 2002.)
Smooth, velvety skin
Tremor of the fingertips
Fatigue
SWEATY PALMS -- This is related to heat intolerance.
Weight loss
Fine brittle hair
RESTLESSNESS -- Some observers noted this during the debates.
Depression
Increased appetite
Changes in sex drive
MUSCLE WEAKNESS, ESPECIALLY IN THE UPPER ARMS AND THIGHS -- The president did drop his 15-pound dog during a handoff from his wife as mentioned above. Also, he has replaced a large part of his running regimen with mountain-bike riding, which, as noted, has resulted in one injurious accident.
Shortened attention span.
HEAT INTOLERANCE -- In the Bush-Kerry camps' agreement for the 2004 debates, one requirement was that the temperature be kept below 70 degrees. This requirement apparently came from the Kerry camp since Sen. Kerry supposedly sweats easily. However, this would also serve Mr. Bush's interest if he has hyperthyroidism.
INCREASED SWEATING
NERVOUSNESS AND IRRITABILITY -- This is one of the symptoms that also has a neurological etiology.
Restless sleep or insomnia -- Mr. Bush does arise at 5 a.m., at least at his ranch.
ERRATIC BEHAVIOR -- Besides hyperthyroidism, this obiously also is a symptoms of Wernick-Korsakoff syndrome (alcoholic syndrome) as well as various dementias including multi-infarct dementia.
CONCLUSION
The president apparently uses a wearable defibrillator, a device to stop heart arrhythmia, as seen in photographs. He has had a sudden fainting spell and other symptoms of atrial fibrillation (AF) and has a genetic tendency for it. Some observers have noted neurological and psychological irregularities and other evidence of stroke, which is a possible result of AF. Some of these irregularities could be caused by Wernicke-Korsakoff's, a disease of inveterate alcoholics, or some other organic brain disease. The president has an even stronger genetic predisposition for hyperthyroidism and some symptoms of it, including the heartbeat arrhythmia. Only his doctors know for sure.
by C L Hallmark
Sunday, Dec. 26, 2004 at 3:08 AM
lifevest_control_5_calls.jpg, image/jpeg, 269x150
by C L Hallmark
Sunday, Dec. 26, 2004 at 3:08 AM

t-shirt_1_calls.jpg, image/jpeg, 514x335
by C L Hallmark
Sunday, Dec. 26, 2004 at 3:08 AM

jan_2002_bush_pretzel.jpg, image/jpeg, 220x170
by C L Hallmark
Sunday, Dec. 26, 2004 at 3:08 AM

bush_tia_droop_2.jpg, image/jpeg, 150x200
by meat inspector
Sunday, Dec. 26, 2004 at 6:33 AM
I feel so sorry...
...that this defective is the best the Republicans can come up with as a semi talking, self propelled, meat puppet. Long live the chimp.
by more rational
Sunday, Dec. 26, 2004 at 11:38 AM
After strokes, people get that droopy face, and have a few speech impairments. Speech may be slurred. Word choice may be affected, and the person may mistakenly choose a word that starts with the same letter or sound. For example, "hand me the cat" instead of "hand me the cup". They don't catch the error until after they've said the word.
Also, higher order thinking seems to be impaired, in the stroke victims I've met. They lose some sense of sentimentality, or subtlety of feeling. It can be refreshing, because they live "in the moment," and they really appreciate happy moments, but you can't count on them to really be sympathetic to others' pain. The lose interest in reading, if they can read at all.
I've had two relatives die from strokes, and have met a few victims who are still living. I'll probably have my own in a few more decades. Oh well.
by Meyer London
Tuesday, Dec. 28, 2004 at 9:41 PM
I think the device is an artificial, battery-powered brain. Even if it is powered only by two AA batteries, they probably still deliver way more power than his original brain cells.
by more rational
Tuesday, Dec. 28, 2004 at 11:48 PM
Indeed, computers do get more powerful each year.
I saw these old electronic kits that made a simple battery powered version of the "mysterious 8-ball" executive decisionmaking tool. It was a lot faster than flipping that old ball upside down over and over.
by Rich Murray
Monday, Jan. 03, 2005 at 8:16 PM
rmforall@comcast.net 505-501-2298 1943 Otowi Road, Santa Fe, New Mexico 87505
2005.01.04 Hello Clayton L. Hallmark,
[ Concerned that important information for the health of the President
somehow reach responsible experts, I am sending this to researchers
connected with National Naval Medical Center whose email addresses were in
PubMed since May, 2003. ]
[ http://la.indymedia.org/news/2004/12/120496.php
President George W. Bush: Will He Have to Step Aside for President Cheney?
(Health)
George W. Bush apparently is wearing a medical device for "persons at risk
of cardiac arrest." It is a LifeVest wearable defibrillator. He started
using it sometime after his January 2002 fainting spell, which was
attributed to choking. Based on photos showing him wearing the device, one
can conclude the fainting was due to atrial fibrillation (AF), which his
father also had.
lifevest_duo_back_2.jpg, image/jpeg, 548x236
PHOTOS Show George W. Bush Seriously Ill Physically
His father's AF was caused by Graves' hyperthyroidism, which Barbara Bush
also has. Bush Jr likely has AF and, less likely, Graves', based on his
family history and symptoms. The AF may have caused a stroke or TIA
(mini-stroke), of which physicians watching the debates detected symptoms.
Observers have noted psychological symptoms consistent with this and with
Wernicke-Korsakoff disease. NOTE: If the photos have not uploaded to this
site, see also: http://colombia.indymedia.org/news/2004/12/20372.php. ]
Thanks for your detailed, competent article on the possibility that
President Bush has Graves Disease, as do both his parents. I have published
on the Net several reviews with much relevant information regarding the risk
to him and other leaders from aspartame and other methanol (formaldehyde,
formic acid) sources.
http://groups.yahoo.com/group/aspartameNM/message/876
hyperthyroidism (Graves disease) in George and Barbara Bush, 1991--
aspartame toxicity? Roberts 1997: Murray 2002.10.09 rmforall
In mutual service,
Rich Murray, MA Room For All rmforall@comcast.net
1943 Otowi Road, Santa Fe, New Mexico 87505 USA 505-501-2298
http://groups.yahoo.com/group/aspartameNM/messages
137 members, 1,142 posts in a public searchable archive
*****************************************************************
http://groups.yahoo.com/group/aspartameNM/message/1091
Justin Dumais, 25, Olympic diver, business graduate, pilot, healed of Graves
disease (hyperthyroidism) by giving up aspartame: Roberts: Murray
2004.06.11 rmforall
"The disease most often strikes middle-aged women.
"A 25-year-old male elite athlete is about as far from the stereotypical
Graves patient as you can get," he says.
Now, he has his doctors baffled.
He began taking medication in February but continued doing his own research.
He found a nutritionist who suggested he cut aspartame, an artificial
sweetener found in products such as diet soda, from his diet.
In mid-March, he quit diet soda and his medication.
Now, Dumais feels so much better, he questions whether he really has Graves'
disease, which has no known cure."
http://www.usatoday.com/sports/olympics/athens/swimming/2004-06-10-dumais_x.htm
Posted 6/10/2004 10:03 PM Updated 6/11/2004 1:04 PM
Disease diagnosis doesn't deter diver By Vicki Michaelis, USA TODAY
*****************************************************************
http://groups.yahoo.com/group/aspartameNM/message/1092
Janet Starr Hull, who also had Graves disease in 1991, told Justin Dumais to
quit aspartame: Murray 2004.06.12 rmforall
From: "Dr. Janet Starr Hull" <jshull@sweetpoison.com>
To: "Rich Murray" <rmforall@comcast.net>
Subject: Re: Justin Dumais, 25, Olympic diver, business graduate,
pilot,healed of Graves disease (hyperthyroidism) by giving up
aspartame:Roberts: Murray 2004.06.11 rmforall
Date: Saturday, June 12, 2004 6:37 PM
Thanks so much for circulating Justin's wonderful case history. The
nutritionist he found was myself, after he had read my book SWEET POISON.
His case is identical to mine, and he followed my experience and my 10 Step
Detox program exactly as I did, and his Grave's Disease disappeared within
60 days. We have been working closely for the past few months.
Keep spreading this wonderful news. As Justin's story is yet another case
identical to mine that proves neither of us ever had Grave's Disease --
merely aspartame poisoning.
All the best, Janet Hull
Dr. Janet Starr Hull, PhD, CN jshull@sweetpoison.com
Hair Analysis Program: http://www.hairanalysisprogram.com
http://www.sweetpoison.com/
http://www.janethull.com/about/index.php
http://www.detoxprogram.net/
http://www.detoxprogram.net/about-dr-janet-hull.php
*****************************************************************
Fully 11% of aspartame is methanol [ wood alcohol ] -- 1,120 mg aspartame
in 2 L diet soda, almost six 12-oz cans, gives 123 mg methanol (wood
alcohol) -- the same amount that produces hangover from red wine.
The methanol is immediately released into the body after drinking --
as are the even larger levels of methanol locked up in complex pectin
molecules inside
many fruits and vegetables, released by degradation by bacteria in the
colons of many people.
Within hours, the body turns much of the methanol into formaldehyde, and
then much of that into formic acid, both of which in time are partially
eliminated as carbon dioxide and water.
This long-term low-level chronic toxic exposure leads to typical patterns of
increasingly severe complex symptoms, starting with headache, fatigue, joint
pain, irritability, memory loss, rashes, and leading to vision and eye
problems, and even seizures. In many cases there is addiction. Probably
there are immune system disorders, with a hypersensitivity to these toxins
and other chemicals.
groups.yahoo.com/group/aspartameNM/message/1065
politicians and celebrities hooked on diet sodas (aspartame):
Murray 2004.03.24 rmforall
groups.yahoo.com/group/aspartameNM/message/1121
diet soda sweetener aspartame [ NutraSweet, Equal, Canderel, E951, Benevia ]
toxicity research: Murray 2004.10.11 rmforall
Rich Murray, MA Room For All rmforall@comcast.net
1943 Otowi Road, Santa Fe, New Mexico 87505 USA 505-501-2298
groups.yahoo.com/group/aspartameNM/messages
137 members, 1,125 posts in a public searchable archive Moderator
[ BS physics and history MIT 1964,
MA psychology Boston University Graduate School 1967, 1988 to present,
full-time home hospice care giver in Santa Fe ]
**************************************************************
http://groups.yahoo.com/group/aspartameNM/message/927
Donald Rumsfeld, 1977 head of Searle Corp., got aspartame FDA approval:
Turner: Murray 2002.12.23 rmforall
http://groups.yahoo.com/group/aspartameNM/message/1016
President Bush & formaldehyde (aspartame) toxicity: Ramazzini Foundation
carcinogenicity results Dec 2002: Soffritti: Murray 2003.08.03 rmforall
http://groups.yahoo.com/group/aspartameNM/message/874
re "dry drunk": Bisbort: danger to President Bush from aspartame toxicity:
Murray: 2002.02.24 2002.09.29 rmforall
http://www.willthomas.net/911/Bush/
Is Bush Nuts?: William Thomas willthomas.net 2004
http://groups.yahoo.com/group/aspartameNM/message/1101
John Edwards gives up Diet Coke: The Cult of Diet Coke, Eric Gillin:
Murray 2004.07.12 rmforall
http://groups.yahoo.com/group/aspartameNM/message/1102
John Edwards still drinks Diet Coke (aspartame): TIME Europe July 19 issue:
Murray 2004.07.12 rmforall
http://groups.yahoo.com/group/aspartameNM/message/876
hyperthyroidism (Graves disease) in George and Barbara Bush, 1991--
aspartame toxicity? Roberts 1997: Murray 2002.10.09 rmforall
http://www.dorway.com/upipart1.txt
http://groups.yahoo.com/group/aspartameNM/message/262
aspartame expose 96K Oct 1987 Part 1/3: Gregory Gordon, UPI reporter:
Murray 2000.07.10 rmforall
http://www.dorway.com/enclosur.html
http://groups.yahoo.com/group/aspartameNM/message/53
aspartame history Part 1/4 1964-1976: Gold: Murray 1999.11.06 rmforall
http://groups.yahoo.com/group/aspartameNM/message/928
revolving door, Monsanto, FDA, EPA: NGIN: Murray 2002.12.23 rmforall
***************************************************************
I have been writing careful reviews of mostly mainstream medical research on
aspartame toxicity for six years. In recent months I have become aware that
evidence strongly shows that substantial methnol and thus formaldehyde and
formic acid are released into humans from degradation of the pectins from
fruits and vegetables by bacteria in the colon in many people. The
biochemical dispositions of formaldehyde are actually largely unknown,
according to the expert comprehensive review by Bouchard M et al, 2001.
Research on hangovers, largely caused by the conversion of methanol impurity
in alcohol drinks into formaldehyde after about eight hours, shows that a
quarter to a half of those who get inebriated do not get hangovers. This
shows very large individual variation in vulnerability to formaldehyde
toxicity, so as a corollary, probably there will be many who are not
markedly vulnerable to aspartame.
I am guessing that evolution has given humans the ability to store the large
amounts of formaldehyde generated from pectins and to use them to attack
pathogens. So far, I have not found any strong research to support this
hypothesis. I hope to write a useful summary in the next few weeks.
There are many substances, such as folic acid, that protect against
formaldehyde toxicity.
http://groups.yahoo.com/group/aspartameNM/message/1143
antiseptic? antifungal? antiviral? methanol (formaldehyde, formic acid)
disposition: Bouchard M et al, full plain text, 2001: substantial sources
are degradation of fruit pectins, liquors, aspartame, smoke: Murray
2005.01.04 rmforall
This long, complex review presents mainstream evidence for several
ubiquitous, substantial sources of methanol and its inevitable chain of
products, formaldehyde and formic acid, which I will initialize as "MCC",
for Methanol Chain Compounds.
Monte WC in his seminal summary review (1984) mentions that humans are
uniquely vulnerable to the conversion of methanol into formaldehyde:
"Fruit and vegetables contain pectin with variable methyl ester content.
However, the human has no digestive enzymes for pectin (6, 25)
particularly the pectin esterase required
for its hydrolysis to methanol (26)."
"Humans, due perhaps to the loss of two enzymes during evolution, are
more sensitive to methanol than any laboratory animal; even the monkey
is not generally accepted as a suitable animal model (42)."
"The methyl ester bond of phenyalanine is the first
to cleave due to its susceptibility to pancreatic enzymes (40).
This is highly unusual; the methyl esters
associated with pectin for instance
are completely impervious to all human digestive enzymes (6)."
"The greater toxicity of methanol to man is deeply rooted in the limited
biochemical pathways available to humans
for detoxification. The loss of uricase (EC 1.7.3.3.),
formyl-tetrahydrofolate synthetase (EC 6.3.4.3.) (42)
and other enzymes (18) during evolution sets man apart from all
laboratory animals including the monkey (42)."
"The importance of ethanol as an antidote to methanol toxicity in humans
is very well established in the literature (46, 55). The timely
administration of ethanol is still considered a vital part of methanol
poisoning management (11, 12, 19, 20, 50). Ethanol slows the rate of
methanol's conversion to formaldehyde and formate, allowing the body
time to excrete methanol in the breath and urine. Inhibition is seen in
vitro even when the concentration of ethyl alcohol was only 1/16th that
of methanol (62). The inhibitory effect
is a linear function of the log of the
ethyl alcohol concentration, with a 72% inhibition rate at only
a 0.01 molar concentration of ethanol (2, 46).
Oxidation of methanol, like that of ethanol, proceeds independently of
the blood concentration, but at a rate only one seventh (20) to one
fifth (12) that of ethanol.
Folacin may play an important role in the metabolism of methanol by
catalyzing the elimination of formic acid (41). If this process proves
to be as protective for humans as has been shown in other organisms
(50, 38) it may account, in part, for the tremendous variability of
human responses to acute methanol toxicity. Folacin is a nutrient
often found lacking in the normal human diet, particularly during
pregnancy and lactation (14)."
It is well known that our primate ancestors were highly adapted to a diet of
fruits and vegetables, and thus had the enzyme systems to prevent toxicity
from the inevitable methanol content and from methanol from the degradation
of pectins by bacteria in the colon.
Humans have been living in groups in lifelong close proximity with fire and
smoke, a potent source of formaldehyde, for about 2 million years. Fire has
ever since been essential for survival, as has been intimate enclosed group
living, especially as homo erectus, Neanderthals, and moderns successively
adapted to very cold habitats.
Yet formaldehyde is among the most potent of toxins, and cumulative to boot.
Yet intimate enclosed group living in a variety of environments promotes
extreme exposure to a variety of contagious, infectious diseases. And yet,
humans lack two enzymes that protect against Methanol Chain Compounds
toxicities. What is an obvious evolutionary explanation for this?
MCC toxicities must serve to prevent and treat contagious infections from
bacteria, fungi, parasites, and possibly viruses. This would generate a
potent positive selection pressure to cause humans to evolve the ability to
have increased MCC exposures, and to be multiply adapted to tolerate MC
toxicities.
Wine and beer serve throughout history to protect against water bourne
pathogens. For centuries formaldehyde has been used to protect medical
scientists from highly infected cadaver tissues. What is the scientific
literature about MCC and the various groups of contagious infectious agents?
It is a testable hypothesis as to whether MCC in many types of people, with
the inevitable complex variations of genetics and diet, impede many simple
infectious agents more than they harm critical body processes in complex
human cells.
It may be that MCC are important unexamined co-factors that strongly affect
research and treatment of many infectious diseases.
We might find, for instance, that in many humans some infections cause
reduction of folic acid or folate levels, and thus increased MCC levels.
Many traditional societies treat diseases with exposure to smoke, whether in
a hut with a wood fire, or in a temple with incense. Likewise, alcohol
drinks have been widely used as remedies. Did the daily ration of grog in
the
British Navy serve to reduce infections in the close and dirty confines of
life on wooden ships? In the trenches of World War I, the British also had a
daily ration -- were their rates of infection lower than for troops that had
little liquor?
These questions throw an entirely new light, expansive, tantalizing, and
unifying, on the often contentious and poorly researched issues of MCC
toxicity, especially the aspartame controversy. It would also be ironic,
but typical of the actual complex evolution of science, for tobacco and wood
smoke to be shown to have some benefits for infectious diseases.
http://groups.yahoo.com/group/aspartameNM/message/1140
EPA Preliminary Remedial Goals, PRGs, 2003 Oct, air and tap water --
methanol, formaldehyde, formic acid -- not mentioned is methanol from
aspartame, dark wines and liquors: Murray 2004.11.20 rmforall
http://groups.yahoo.com/group/aspartameNM/message/1141
Nurses Health Study can quickly reveal the extent of aspartame (methanol,
formaldehyde, formic acid) toxicity: Murray 2004.11.21 rmforall
The Nurses Health Study is a bonanza of information about the health of
probably hundreds of nurses who use 6 or more cans daily of diet soft
drinks -- they have also stored blood and tissue samples from their immense
pool of subjects.
Dark wines and liquors, as well as aspartame, provide similar levels of
methanol, above 100 mg daily, for long-term heavy users. Methanol is
inevitably largely turned into formaldehyde, and thence largely into formic
acid. Both products are toxic, and at this level of use, about 2 L daily,
almost six 12-oz cans of diet drink, are above recent lifetime EPA [ PRG ]
safety limits in tap water for methanol and formaldehyde of respectively,
for a 60 kg person, 30 mg and 9 mg daily.
The immediate health effects for dark wines and liquors are the infamous
"morning after" hangover, for which many informed experts cite as the major
cause the conversion of the methanol impurity, over one part in ten thousand
(red wine has 128 mg/L methanol), into formaldehyde and formic acid.
Everyone knows the complex progression of symptoms at this level of
long-term, chronic toxicity.
Aspartame reactors have a very similar progression.
If 1% of all people exposed to alcohol and/or aspartame are heavy users with
symptoms, then there would easily be about 2 million cases in the USA alone.
This is a public health emergency.
At the very least, professionals and the public should be alerted to
investigate their own exposure, and be given a chance to try a very safe,
simple, inexpensive treatment for complex, intractable, progressive
symptoms -- reducing or eliminating their intake.
There are as well, many safe substances that prevent or treat the
toxicities -- for example, high folic acid levels expedite the elimination
of formaldehyde.
These toxicities are largely uncontrolled co-factors that affect every
disease and must confuse and impede many health research programs on all
levels.
People in high-pressure, critical occupations, such as pilots, nuclear plant
operators, and national leaders, should certainly be alerted.
Also, two careful studies show substantial methanol release from degradation
of pectins by bacteria in the colon from fruits and vegetables -- a topic
that deserves careful, thorough research.
Due to my bias, based on detailed reviews by Monte WC (1984) and by Mark D.
Gold (2003), for months I have been discounting the startlingly high
methanol levels reported in the abstract for Lindinger W (1997). I have
been reducing the values in their abstract from g to mg, an unwarrented
"correction" by a factor of a thousand, only to find that the full text
study and their many related studies supply expert, robust results:
Alcohol Clin Exp Res. 1997 Aug; 21(5): 939-43.
Endogenous production of methanol after the consumption of fruit.
Lindinger W, Taucher J, Jordan A, Hansel A, Vogel W.
Institut fur Ionenphysik, Leopold Franzens Universitat Innsbruck, Austria.
After the consumption of fruit, the concentration of methanol in the human
body increases by as much as an order of magnitude.
This is due to the degradation of natural pectin (which is esterified with
methyl alcohol) in the human colon.
In vivo tests performed by means of proton-transfer-reaction mass
spectrometry show that consumed pectin in either a pure form (10 to 15 g)
or a natural form (in 1 kg of apples) induces a significant increase of
methanol in the breath (and by inference in the blood) of humans.
The amount generated from pectin (0.4 to 1.4 g)
is approximately equivalent to the total daily endogenous production
(measured to be 0.3 to 0.6 g/day)
or that obtained from 0.3 liters of 80-proof brandy
(calculated to be 0.5 g). [ 1667 mg methanol per liter of brandy ]
This dietary pectin may contribute to the development
of nonalcoholic cirrhosis of the liver. PMID: 9267548
Alcohol Clin Exp Res. 1995 Oct; 19(5): 1147-50.
Methanol in human breath.
Taucher J, Lagg A, Hansel A, Vogel W, Lindinger W.
Institut fur Ionenphysik, Universitat Innsbruck, Austria.
Using proton transfer reaction-mass spectrometry for trace gas analysis of
the human breath, the concentrations of methanol and ethanol have been
measured for various test persons consuming alcoholic beverages and various
amounts of fruits, respectively.
The methanol concentrations increased from a natural (physiological) level
of approximately 0.4 ppm up to approximately 2 ppm a few hours after eating
about 1/2 kg of fruits,
and about the same concentration was reached after drinking of 100 ml brandy
containing 24% volume of ethanol and 0.19% volume of methanol.
[ 24 ml = 61 g ethanol, and 0.19 ml = 0.34 g = 340 mg methanol ]
PMID: 8561283
I urge Channing Laboratory and its participating universities to rapidly
mount an in-house study to study the Nurses Health Study database for the
hundreds of nurses who are long-term users, above 6 cans diet drinks daily,
for correlations with every disease, as well as ubiquitous co-factors like
wine and liquor, cigarette smoke, and fruits and vegetables. It could
vastly serve the world public health to make the initial findings widely
available immediately. The
disparaged issue of aspartame toxicity could be swiftly made legitimate, and
the resulting progress on all levels remarkably accelerated.
A single scientist could do this.
Comments pro and con are welcome. A convenient venue would be the
newsgroup: bionet.toxicology.
Rich Murray, MA Room For All rmforall@comcast.net
1943 Otowi Road, Santa Fe, New Mexico 87505 USA 505-501-2298
http://groups.yahoo.com/group/aspartameNM/messages
137 members, 1,142 posts in a public searchable archive
**************************************************************
http://groups.yahoo.com/group/aspartameNM/message/957
safety of aspartame Part 1/2 12.4.2: EC HCPD-G SCF:
Murray 2003.01.12 rmforall EU Scientific Committee on Food, a whitewash
http://groups.yahoo.com/group/aspartameNM/message/1045
http://www.holisticmed.com/aspartame/scf2002-response.htm
Mark Gold exhaustively critiques European Commission Scientific
Committee on Food re aspartame ( 2002.12.04 ): 59 pages, 230 references
"C. Public Relations, Aspartame, Methanol, and Formaldehyde
Before we discuss what little the Committee did say related to aspartame and
formaldehyde, it is important to answer all of the typical public relations
statements from the manufacturer and their consultants who claim there is no
problem with aspartame and formaldehyde. The answers provided below will be
brief. Much more detailed and referenced answers can be found at ATIC (2001)
on the Internet at:
[ http://www.holisticmed.com/aspartame/abuse/methanol.html ].
Chart of Aspartame Manufacturer Public Relations Statements
Related to Methanol and Formaldehyde
Manufacturer Claim --- Independent Response
Methanol is found in fruits and alcoholic beverages at higher levels than in
aspartame products. --- Alcoholic beverages contain large amounts of
ethanol (a protective factor) which allows methanol to be excreted before
much of it is converted into formaldehyde (Leaf 1952, Liesivuori 1991, Roe
1982).
Fruit juices have protective factors as well that prevent formaldehyde
poisoning. Fruit juices produce enough methanol to "qualify as significantly
methanol-contaminated liquor" (Lindinger 1997) -- more methanol than what
causes chronic health problems in occupational exposure (Kazeniac 1970,
Kavet 1990, Frederick 1984, Kingsley 1954-55). Since we do not see chronic
poisoning from fruit juices, they must contain protective factors as well.
Fruit juices have ethanol as well as other possible protective factors."
http://groups.yahoo.com/group/aspartameNM/message/870
Aspartame: Methanol and the Public Interest 1984: Monte:
Murray 2002.09.23 rmforall
Dr. Woodrow C. Monte Aspartame: methanol, and the public health.
Journal of Applied Nutrition 1984; 36 (1): 42-54.
(62 references) Professsor of Food Science [retired 1992]
Arizona State University, Tempe, Arizona 85287 woodymonte@xtra.co.nz
***********************************************************
[ Comments by Rich Murray are in square bracketts. Without changing text,
except for omitting long equations, figures, and tables, spacing has been
added to give emphasis and increase readability. Following are some
specific extracts. ]
"That substantial amounts of methanol metabolites or by-products are
retained for a long time is verified by Horton et al. (1992) who estimated
that 18 h following an iv injection of 100 mg/kg of 14C-methanol in male
Fischer-344 rats, only 57% of the dose was eliminated from the body.
From the data of Dorman et al. (1994) and Medinsky et al. (1997), it can
further be calculated that 48 h following the start of a 2-h inhalation
exposure to 900 ppm of 14C-methanol vapors in female cynomolgus monkeys,
only 23% of the absorbed 14C-methanol was eliminated from the body.
These findings are corroborated by the data of Heck et al. (1983) showing
that 40% of a 14C-formaldehyde inhalation dose remained in the body 70 h
postexposure."
"Exposure to methanol also results from the consumption of certain
foodstuffs (fruits, fruit juices, certain vegetables, aspartame sweetener,
roasted coffee, honey) and alcoholic beverages (Health Effects Institute,
1987; Jacobsen et al., 1988)."
[ It's unusual for a mainstream journal article to mention "aspartame
sweetener" and "alcoholic beverages" to be methanol sources.
"However, the severe toxic effects are usually associated with the
production and accumulation of formic acid, which causes metabolic acidosis
and visual impairment that can lead to blindness and death at blood
concentrations of methanol above 31 mmol/l (Røe, 1982; Tephly and McMartin,
1984; U.S. DHHS, 1993).
Although the acute toxic effects of methanol in humans are well documented,
little is known about the chronic effects of low exposure doses, which are
of interest in view of the potential use of methanol as an engine fuel and
current use as a solvent and chemical intermediate.
Gestational exposure studies in pregnant rodents (mice and rats) have also
shown that high methanol inhalation exposures (5000 or 10,000 ppm and more,
7 h/day during days 6 or 7 to 15 of gestation) can induce birth defects
(Bolon et al., 1993; IPCS, 1997; Nelson et al., 1985)."
"The corresponding average elimination half-life of absorbed methanol
through metabolism to formaldehyde was estimated to be 1.3, 0.7-3.2, and 1.7
h."
[ This shows for ingested methanol from the readily released 11% methanol
component of aspartame diet sodas, that by three half-lives,
3 X 1.7 h = 5.1 hr, 7/8 = 88 % of the methanol would be substantially turned
into formaldehyde.
In dark wines and liquors, the conversion of methanol impurity, about one
part in ten thousand, into formaldehyde and then formic acid is prevented
for many hours, as the responsible enzyme is taken up by the remaining
ethanol. When after many hours all the ethanol is metabolized, the
conversion of the remaining methanol into formaldehyde and formic acid is
the major cause of the many difficult symtoms of "morning after" hangover. ]
"Inversely, in monkeys and in humans, a larger fraction of body burden of
formaldehyde is rapidly transferred to a long-term component.
The latter represents the formaldehyde that (directly or after oxidation to
formate) binds to various endogenous molecules..."
"Animal studies have reported that systemic methanol is eliminated mainly by
metabolism (70 to 97% of absorbed dose) and only a small fraction is
eliminated as unchanged methanol in urine and in the expired air (< 3-4%)
(Dorman et al., 1994; Horton et al., 1992).
Systemic methanol is extensively metabolized by liver alcohol dehydrogenase
and catalase-peroxidase enzymes to formaldehyde, which is in turn rapidly
oxidized to formic acid by formaldehyde dehydrogenase enzymes (Goodman and
Tephly, 1968; Heck et al., 1983; Røe, 1982; Tephly and McMartin, 1984).
Under physiological conditions, formic acid dissociates to formate and
hydrogen ions.
Current evidence indicates that, in rodents, methanol is converted mainly by
the catalase-peroxidase system whereas monkeys and humans metabolize
methanol mainly through the alcohol dehydrogenase system (Goodman and
Tephly, 1968; Tephly and McMartin, 1984).
Formaldehyde, as it is highly reactive, forms relatively stable adducts with
cellular constituents (Heck et al., 1983; Røe, 1982)."
"The whole body loads of methanol, formaldehyde, formate, and unobserved
by-products of formaldehyde metabolism were followed.
Since methanol distributes quite evenly in the total body water, detailed
compartmental representation of body tissue loads was not deemed necessary."
"According to model predictions, congruent with the data in the literature
(Dorman et al., 1994; Horton et al., 1992), a certain fraction of
formaldehyde is readily oxidized to formate, a major fraction of which is
rapidly converted to CO2 and exhaled, whereas a small fraction is excreted
as formic acid in urine.
However, fits to the available data in rats and monkeys of Horton et al.
(1992) and Dorman et al. (1994) show that, once formed, a substantial
fraction of formaldehyde is converted to unobserved forms.
This pathway contributes to a long-term unobserved compartment.
The latter, most plausibly, represents either the formaldehyde that
(directly or after oxidation to formate) binds to various endogenous
molecules (Heck et al., 1983; Røe, 1982)
or is incorporated in the tetrahydrofolic-acid-dependent one-carbon pathway
to become the building block of a number of synthetic pathways (Røe, 1982;
Tephly and McMartin, 1984).
That substantial amounts of methanol metabolites or by-products are retained
for a long time is verified by Horton et al. (1992) who estimated that 18 h
following an iv injection of 100 mg/kg of 14C-methanol in male Fischer-344
rats, only 57% of the dose was eliminated from the body.
From the data of Dorman et al. (1994) and Medinsky et al. (1997), it can
further be calculated that 48 h following the start of a 2-h inhalation
exposure to 900 ppm of 14C-methanol vapors in female cynomolgus monkeys,
only 23% of the absorbed 14C-methanol was eliminated from the body.
These findings are corroborated by the data of Heck et al. (1983) showing
that 40% of a 14C-formaldehyde inhalation dose remained in the body 70 h
postexposure.
In the present study, the model proposed rests on acute exposure data, where
the time profiles of methanol and its metabolites were determined only over
short time periods (a maximum of 6 h of exposure and a maximum of 48 h
postexposure).
This does not allow observation of the slow release from the long-term
components.
It is to be noted that most of the published studies on the detailed
disposition kinetics of methanol regard controlled short-term (iv injection
or continuous inhalation exposure over a few hours) methanol exposures in
rats, primates, and humans (Batterman et al., 1998; Damian and Raabe, 1996;
Dorman et al., 1994; Ferry et al., 1980; Fisher et al., 2000; Franzblau et
al., 1995; Horton et al., 1992; Jacobsen et al., 1988; Osterloh et al.,
1996; Pollack et al., 1993; Sedivec et al., 1981; Ward et al., 1995; Ward
and Pollack, 1996).
Experimental studies on the detailed time profiles following controlled
repeated exposures to methanol are lacking."
"Thus, in monkeys and plausibly humans, a much larger fraction of body
formaldehyde is rapidly converted to unobserved forms rather than passed on
to formate and eventually CO2."
"However, the volume of distribution of formate was larger than that of
methanol, which strongly suggests that formate distributes in body
constituents other than water, such as proteins.
The closeness of our simulations to the available experimental data on the
time course of formate blood concentrations is consistent with the volume of
distribution concept (i.e., rapid exchanges between the nonblood pool of
formate and blood formate)."
"Also, background concentrations of formate are subject to wide
interindividual variations (Baumann and Angerer, 1979; D'Alessandro et al.,
1994; Franzblau et al., 1995; Heinrich and Angerer, 1982; Lee et al., 1992;
Osterloh et al., 1996; Sedivec et al., 1981)."
[ There's an on-going debate as to how much of methanol toxicity and
genotoxicity is due to its formaldehyde or formic acid products, along with
a dearth of evidence about the actual biochemical disposition in specific
tissues of people exposed long-term to chronic doses, as in the case of
alcoholics or aspartame reactors.
Fully 11% of aspartame is methanol -- 1,120 mg aspartame in 2 L diet soda,
almost six 12-oz cans, gives 123 mg methanol (wood alcohol). However,
about 30% of the methanol remains in the body as cumulative durable toxic
metabolites of formaldehyde and formic acid, 37 mg daily, a gram every
month, accumulating in and affecting every tissue.
If only 10% of the methanol accumulates daily as formaldehyde, that would
give 12 mg daily formaldehyde accumulation -- about 60 times more than the
0.2 mg from 10% retention of the 2 mg EPA daily limit for formaldehyde in
drinking water.
Bear in mind that the EPA limit for formaldehyde in drinking water is
1 ppm, or 2 mg daily for a typical daily consumption of 2 L of water.
http://groups.yahoo.com/group/aspartameNM/message/835
ATSDR: EPA limit 1 ppm formaldehyde in drinking water July 1999:
Murray 2002.05.30 rmforall
This is the same limit published May 2, 2002 for California.
http://groups.yahoo.com/group/aspartameNM/message/1108
faults in 1999 July EPA 468-page formaldehyde profile:
Elzbieta Skrzydlewska PhD, Assc. Prof., Medical U. of Bialystok, Poland,
abstracts -- ethanol, methanol, formaldehyde, formic acid, acetaldehyde,
lipid peroxidation, green tea, aging, Lyme disease:
Murray 2004.08.08 rmforall
Herein I offer abstracts and three full texts of dozens of studies by a
world-class biochemist and her associates, mostly experiments with rats, on
ethanol toxicity since 1984 and methanol toxicity since 1993. Enough
details are provided to show the competency and credibility of E.
Skrzydlewska and her colleagues over two decades, and to make access to
their literature more convenient for professionals.
It is important that many of her studies suggest that many safe substances
may prevent or treat toxicity from methanol and its inevitable toxic human
body products, formaldehyde and formic acid:
N-acetylcysteine (2000); U-83836E containing a trolox ring (1997);
green tea (2004); vitamins E, C, A, and beta-carotene (2004);
glutathione (2001); N-Acetylcysteine (NAC) (2001); melatonin (2001);
low and medium levels of cysteine (1990).
http://taylorandfrancis.metapress.com/openurl.asp?genre=article&eissn=1537-6524&volume=13&issue=4&spage=277
Toxicology Mechanisms and Methods
Publisher: Taylor & Francis Health Sciences, part of the Taylor & Francis
Group Issue: Volume 13, Number 4 / Oct-Dec 2003 Pages: 277 - 293
Toxicological and Metabolic Consequences of Methanol Poisoning
Elzbieta Skrzydlewska, Assoc. Professor, MSc, PhD,
Deputy Dean of Faculty of Pharmacy,
Head of Department of Analytical Chemistry, Medical University of Bialystok,
Mickiewicza 2A 15-230 Bialystok 8, P.O. Box 14, Poland
skrzydle@amb.ac.bialystok.pl
http://www.amb.edu.pl/en/sites/university.html dzss@amb.edu.pl
Kilinskiego 1 15-089 Bialystok, Poland fax (48 85)7485408
Abstract:
Methanol, when introduced into all mammals, is oxidized into formaldehyde
and then into formate, mainly in the liver.
Such metabolism is accompanied by the formation of free radicals.
In all animals, methanol oxidation, which is relatively slow, proceeds via
the same intermediary stages, usually in the liver,
and various metabolic systems are involved in the process, depending on the
animal species.
In nonprimates, methanol is oxidized by the catalase-peroxidase system,
whereas in primates, the alcohol dehydrogenase system takes the main role in
methanol oxidation.
The first metabolite (formaldehyde is rapidly oxidized by formaldehyde
dehydrogenase) is the reduced glutathione (GSH)-dependent enzyme.
Generated formic acid is metabolized into carbon dioxide with the
participation of H4folate and two enzymes, 10-formyl H4folate synthetase and
dehydrogenase,
whereas nonprimates oxidize formate efficiently.
Humans and monkeys possess low hepatic H4folate and 10-formyl H4folate
dehydrogenase levels
and are characterized by the accumulation of formate after methanol
intoxication.
The consequences of methanol metabolism and toxicity distinguish the human
and monkey from lower animals.
Formic acid is likely to be the cause of the metabolic acidosis and ocular
toxicity in humans and monkeys,
which is not observed in most lower animals.
Nevertheless, chemically reactive formaldehyde and free radicals may damage
most of the components of the cells of all animal species, mainly proteins
and lipids.
The modification of cell components results in changes in their functions.
Methanol intoxication provokes a decrease in the activity and concentration
of antioxidant enzymatic as well as nonenzymatic parameters,
causing enhanced membrane peroxidation of phospholipids.
The modification of protein structure by formaldehyde as well as by free
radicals results changes in their functions,
especially in the activity of proteolytic enzymes and their inhibitors,
which causes disturbances in the proteolytic-antiproteolytic balance toward
the proteolytics and
enhances the generation of free radicals.
Such a situation can lead to destructive processes because components of the
proteolytic-antiproteolytic system during enhanced membrane lipid
peroxidation may penetrate from blood into extracellular space, and an
uncontrolled proteolysis can occur.
This applies particularly to extracellular matrix proteins.
Keywords: Free Radicals, Methanol Metabolism, Methanol Poisoning,
Proteases, Protease Inhibitors ]
*************************************************************
http://www.toxsci.oupjournals.org/cgi/content/full/64/2/169
Toxicological Sciences 64, 169-184 (2001)
Copyright © 2001 by the Society of Toxicology
BIOTRANSFORMATION AND TOXICOKINETIC
A Biologically Based Dynamic Model for Predicting the Disposition of
Methanol and Its Metabolites in Animals and Humans
Michèle Bouchard *, #,1, bouchmic@magellan.umontreal.ca
Robert C. Brunet, # brunet@dms.umontreal.ca
Pierre-Olivier Droz, #
and Gaétan Carrier* gaetan.carrier@umontreal.ca
* Department of Environmental and Occupational Health, Faculty of Medicine,
Université de Montréal, P.O. Box 6128, Main Station, Montréal, Québec,
Canada, H3C 3J7;
# Institut Universitaire romand de Santé au Travail, rue du Bugnon 19,
CH-1005, Lausanne, Switzerland, and
# Département de Mathématiques et de Statistique and Centre de Recherches
Mathématiques, Faculté des arts et des sciences, Université de Montréal,
P.O. Box 6128, Main Station, Montréal, Québec, Canada, H3C 3J7
NOTES
1 To whom correspondence should be addressed at Département de santé
environnementale et santé au travail, Université de Montréal, P.O. Box 6128,
Main Station, Montréal, Québec, H3C 3J7, Canada. Fax: (514) 343-2200.
E-mail: bouchmic@magellan.umontreal.ca
Received May 10, 2001; accepted August 28, 2001
ABSTRACT
TOP
ABSTRACT
INTRODUCTION
METHOD AND MODEL PRESENTATION
RESULTS
DISCUSSION
APPENDIX
REFERENCES
A multicompartment biologically based dynamic model was developed to
describe the time evolution of methanol and its metabolites in the whole
body and in accessible biological matrices of rats, monkeys, and humans
following different exposure scenarios.
The dynamic of intercompartment exchanges was described mathematically by a
mass balance differential equation system.
The model's conceptual and functional representation was the same for rats,
monkeys, and humans, but relevant published data specific to the species of
interest served to determine the critical parameters of the kinetics.
Simulations provided a close approximation to kinetic data available in the
published literature.
The average pulmonary absorption fraction of methanol was estimated to be
0.60 in rats, 0.69 in monkeys, and 0.58-0.82 in human volunteers.
The corresponding average elimination half-life of absorbed methanol through
metabolism to formaldehyde was estimated to be 1.3, 0.7-3.2, and 1.7 h.
Saturation of methanol metabolism appeared to occur at a lower exposure in
rats than in monkeys and humans.
Also, the main species difference in the kinetics was attributed to a
metabolism rate constant of whole body formaldehyde to formate estimated to
be twice as high in rats as in monkeys.
Inversely, in monkeys and in humans, a larger fraction of body burden of
formaldehyde is rapidly transferred to a long-term component.
The latter represents the formaldehyde that (directly or after oxidation to
formate) binds to various endogenous molecules
or is taken up by the tetrahydrofolic-acid-dependent one-carbon pathway to
become the building block of synthetic pathways.
This model can be used to quantitatively relate methanol or its metabolites
in biological matrices to the absorbed dose and tissue burden at any point
in time in rats, monkeys, and humans for different exposures, thus reducing
uncertainties in the dose-response relationship, and animal-to-human and
exposure scenario comparisons.
The model, adapted to kinetic data in human volunteers exposed acutely to
methanol vapors, predicts that 8-h inhalation exposures ranging from 500 to
2000 ppm, without physical activities, are needed to increase concentrations
of blood formate and urinary formic acid above mean background values
reported by various authors (4.9-10.3 and 6.3-13 mg/liter, respectively).
This leaves blood and urinary methanol concentrations as the most sensitive
biomarkers of absorbed methanol.
Key Words: methanol; formaldehyde; formate; toxicokinetics; modeling;
animals; humans.
Methanol is widely used as an industrial solvent and chemical intermediate
(Kavet and Nauss, 1990).
It has also received serious consideration as an alternative automotive fuel
or fuel additive (Health Effects Institute, 1987).
Inhalation is a major route of human exposure to methanol in the
occupational and general environments although skin exposure can occur in
certain industrial settings (Baumann and Angerer, 1979; Downie et al 1992;
Heinrich and Angerer, 1982; Kawai et al., 1991).
Exposure to methanol also results from the consumption of certain foodstuffs
(fruits, fruit juices, certain vegetables, aspartame sweetener, roasted
coffee, honey) and alcoholic beverages (Health Effects Institute, 1987;
Jacobsen et al., 1988).
The toxic effects of acute exposures to high methanol doses in humans are
well documented (Liesivuori and Savolainen, 1991; Røe, 1982; Tephly and
McMartin, 1984; U.S. DHHS, 1993).
Neurological effects, such as the initial transient depression of the
central nervous system, have generally been reported at blood concentrations
of methanol above 6 mmol/l (U.S. DHHS, 1993).
However, the severe toxic effects are usually associated with the production
and accumulation of formic acid, which causes metabolic acidosis and visual
impairment that can lead to blindness and death at blood concentrations of
methanol above 31 mmol/l (Røe, 1982; Tephly and McMartin, 1984; U.S. DHHS,
1993).
Although the acute toxic effects of methanol in humans are well documented,
little is known about the chronic effects of low exposure doses, which are
of interest in view of the potential use of methanol as an engine fuel and
current use as a solvent and chemical intermediate.
Gestational exposure studies in pregnant rodents (mice and rats) have also
shown that high methanol inhalation exposures (5000 or 10,000 ppm and more,
7 h/day during days 6 or 7 to 15 of gestation) can induce birth defects
(Bolon et al., 1993; IPCS, 1997; Nelson et al., 1985).
The potential deleterious effects of methanol have prompted extensive
research on its uptake and disposition in animals and humans.
This has led to the findings that pulmonary absorption of methanol is very
rapid and absorption fraction ranges from about 60 to 85% depending on the
species (Dorman et al., 1994; Fisher et al., 2000; Horton et al., 1992).
Due to the high water solubility of methanol, the distribution of absorbed
methanol in the tissues of the body is a function of their relative water
content (Sejersted et al., 1983).
Animal studies have reported that systemic methanol is eliminated mainly by
metabolism (70 to 97% of absorbed dose) and only a small fraction is
eliminated as unchanged methanol in urine and in the expired air (< 3-4%)
(Dorman et al., 1994; Horton et al., 1992).
Systemic methanol is extensively metabolized by liver alcohol dehydrogenase
and catalase-peroxidase enzymes to formaldehyde, which is in turn rapidly
oxidized to formic acid by formaldehyde dehydrogenase enzymes (Goodman and
Tephly, 1968; Heck et al., 1983; Røe, 1982; Tephly and McMartin, 1984).
Under physiological conditions, formic acid dissociates to formate and
hydrogen ions.
Current evidence indicates that, in rodents, methanol is converted mainly by
the catalase-peroxidase system whereas monkeys and humans metabolize
methanol mainly through the alcohol dehydrogenase system (Goodman and
Tephly, 1968; Tephly and McMartin, 1984).
Formaldehyde, as it is highly reactive, forms relatively stable adducts with
cellular constituents (Heck et al., 1983; Røe, 1982).
It can also enter, directly or after oxidation to formate, the
tetrahydrofolic-acid-dependent one-carbon pathway to become the building
block of many synthetic pathways (Røe, 1982; Tephly and McMartin, 1984).
The detoxification of formate occurs mainly by a tetrahydrofolate-dependent
multistep pathway to carbon dioxide (CO2) (McMartin et al., 1977; Palese and
Tephly, 1975).
A small percentage of body formate is also eliminated directly in the urine
(Dorman et al., 1994; Horton et al., 1992).
Marked species differences in methanol toxicity and metabolism have been
reported.
Primates and humans appear to be more susceptible to the acute toxicity of
methanol than rodents (Tephly and McMartin, 1984).
This has been mainly attributed to the slower metabolism and elimination
rate of formate in larger species (Tephly and McMartin, 1984).
Based on the available toxicokinetic data of methanol in rats, mice,
monkeys, and humans, toxicokinetic processes were described in the past
using classic 1 to 3 compartmental models with saturable elimination
(Batterman et al., 1998; Damian and Raabe, 1996; Dorman et al., 1994; Nihlén
and Droz, 2000; Pollack and Brouwer, 1996; Pollack et al., 1993; Ward et
al., 1995; Ward and Pollack, 1996).
Physiologically based pharmacokinetic (PBPK) models for methanol in animals
and humans were also developed (Fisher et al., 2000; Horton et al., 1992;
Perkins et al., 1995; Ward et al., 1997).
Recently, a different type of multicompartment modeling approach has been
developed to describe the disposition kinetics of polychlorinated
dibenzo-dioxins and furans (PCDD and PCDFs) (Carrier et al., 1995a,b),
azinphosmethyl and its alkylphosphate metabolites (Carrier and Brunet,
1999), and methyl mercury and its inorganic metabolites (Carrier et al.,
2001a,b).
This type of biologically based dynamic model is a refinement of classic
compartment models, but is closer to biological processes and enables
simulations for a variety of exposure scenarios in different species.
This heuristic approach allows essential characteristics of
intercompartmental transfer processes to be captured using a minimum of
parameters and without the need for extensive knowledge of all the
physiological processes.
The ultimate goal of this approach is to develop a robust human
toxicokinetic model based on human data, thus avoiding as much as possible
uncertainties associated with animal to human extrapolations.
The objective of the present study was to develop and validate such a
biologically based dynamic model to describe the time evolution of methanol
and its metabolites in the whole body, and in accessible biological matrices
(blood, urine, and expired air), and allow links to be made between the
different compartments.
This model is constructed by establishing the overall biological
determinants of methanol disposition in animals and humans, taking into
account the different time-scales involved in the biological processes.
The model parameters specific to the species of interest are then determined
from direct fits to the in vivo time course data of methanol and its
metabolites in blood and excreta (urine and expired air), available in the
published literature.
Model Development
A toxicokinetic, biologically based, dynamic model was developed to describe
the time evolution of methanol biodisposition in the animal (rat and monkey)
and human body.
The modeling process can be described in four steps:
(1) the conceptual and functional representation of the model,
(2) the determination of parameters,
(3) the simulation of the kinetic profile, and
(4) the validation of the model.
Conceptual and functional representation.
The disposition kinetics of methanol and its metabolites following exposure
to methanol was modeled using a multicompartment dynamic system, described
mathematically by a system of coupled differential equations.
The model conceptual and functional representation is depicted in Figure 1.
It aims to be sufficiently detailed to describe the available in vivo data
provided by Horton et al. (1992) on the disposition kinetics of methanol and
its metabolites in rats.
It was then verified that it described equally well the monkey and human
kinetic behavior (Dorman et al., 1994; Osterloh et al., 1996; Sedivec et
al., 1981).
View larger version (30K):
[in this window]
[in a new window]
FIG. 1. Conceptual representation of methanol kinetics.
Symbols are described in Table 1.
The whole body (blood and tissues) and the excretory routes (urine and
exhaled air) were each represented by a compartment.
The whole body loads of methanol, formaldehyde, formate, and unobserved
by-products of formaldehyde metabolism were followed.
Since methanol distributes quite evenly in the total body water, detailed
compartmental representation of body tissue loads was not deemed necessary.
Formaldehyde in the whole body was also represented as a separate
compartment although its metabolism rate is too rapid to allow its
quantification (half-life of about 1.5 min according to McMartin et al.
[1979] and Tephly and McMartin [1984]).
It can be shown that, under such fast breakdown, only formaldehyde
partitioning between formate and other by-products is relevant to the
unfolding of the dynamics.
The respiratory tract was further represented as a separate compartment
since it is the route of entry of inhaled methanol.
Excretion compartments were the methanol in the exhaled air, the urinary
methanol, the urinary formic acid, the CO2 in the exhaled air, and the
excreted unobserved metabolites.
The dynamic of intercompartment exchanges was then described mathematically
by a mass balance differential equation system (see Appendix).
Essentially, the rates of change in the amounts of methanol and its
metabolites in a given compartment were described as the difference between
compartment rates of uptake and loss.
(Symbols used in the functional representation of the model are presented in
Table 1.)
Solving numerically the system of differential equations yielded the time
courses of methanol and its metabolites in the different compartments.
View this table:
[in this window]
[in a new window]
TABLE 1 Symbols Used in the Conceptual and Functional Representation of the
Model
It should also be mentioned that metabolism was considered to follow
Michaelis-Menten kinetics.
However, only in the case of methanol metabolism to formaldehyde was a
saturation constant introduced since, with the exposure dose range used in
the studies on which the model is based, no saturation of formate or CO2
metabolism was apparent (Dorman et al., 1994; Horton et al., 1992; Osterloh
et al., 1996 Sedivec et al., 1981).
Determination of the parameters.
Unknown parameters were estimated individually from a statistical best-fit
to the experimental data specific to the species of interest, by using the
explicit solutions of subsystems of differential equations when possible
(see Appendix). A professional edition of a MathCad software was used for
this purpose (MathSoft Inc., Cambridge, MA).
Rat parameters.
Parameters to be determined were the intercompartment transfer rate
coefficients and metabolism rate constants. Data of Horton et al. (1992) in
male Fischer-344 rats exposed to a single iv dose of 100 mg per kg of body
weight of 14C-methanol (n = 4) were used to determine the rat parameters.
Blood concentration-time profiles (expressed in mg/l) and cumulative urinary
excretion time courses of 14C-methanol and 14C-formate (expressed in µmol)
were determined by these authors as well as the cumulative exhalation time
courses of 14C-methanol and 14CO2 (expressed in µmol).
In the current study, for the fitting of experimental data and to determine
parameters, all the experimental values were converted to burdens expressed
in moles.
It was then verified that the mass balance was maintained at all time
points. Also, reported blood concentration values were converted to whole
body burdens by multiplication by the apparent volume of distribution (Vd).
In rats, the apparent volume of distribution of methanol (VdMeOH) was
determined so that the initial experimental concentration of methanol in
blood at time t = 5 min, when converted in terms of burden, gives the iv
dose (700 µmol) reported by Horton et al. (1992).
Monkey parameters.
To adapt the model to monkey data, only the values of the intercompartment
transfer rates and metabolism constants needed to be modified.
Using the same approach as in rats, transfer parameters values of the
general model solutions were estimated individually by best-fits, using
MathCad, to the available experimental data of Dorman et al. (1994).
These authors exposed 4 adult female cynomolgus monkeys (Macaca
fascicularis, 3-5.5 kg) by inhalation to 900 ppm of 14C-methanol for 2 h.
Blood concentration-time profiles of 14C-methanol and 14C-formate (expressed
in µmol/l) were determined as well as the cumulative urinary excretion of
14C-methanol and 14C-formate 48-h postexposure (expressed in µmol).
The time courses of 14C-methanol and 14CO2 exhalation rates (µmol/min) were
also established.
For the determination of the parameter values, the latter rates were
converted to cumulative excretion.
The pulmonary ventilation rate of female cynomolgus monkeys used in the
model was that reported by Dorman et al. (1994), that is on average 33 l/h
or 0.56 l/min (equivalent to 0.033 m3/h or 0.8 m3/day).
In monkeys, the apparent volume of distribution of methanol was calculated
by best-fit of the following equation to the data observed during the
constant inhalation built up of methanol blood concentration (B(t)):
[ long equation ]
where kelim is the sum of all rates of methanol elimination (metabolism,
exhalation, and urinary excretion).
Human parameters.
When possible, the constants were determined using the available human data.
This includes the pulmonary absorption fraction of methanol, the pulmonary
ventilation rate, the apparent volume of distribution of methanol, the
metabolism rate constant kmet of whole body methanol to formaldehyde, and
the transfer rate constant km of whole body methanol to urine.
The other constant parameters were left as determined in monkeys, which are
considered as good surrogates to humans for the study of methanol kinetics.
Pulmonary absorption fraction of methanol used in the model adapted to
humans was that reported by Sedivec et al. (1981).
The human value was nonetheless close to that determined in rats and
monkeys.
Human pulmonary ventilation rate used in the model was that reported by
Sedivec et al. (1981), that is on average 10.8 l/min.
The apparent volume of distribution of methanol was that reported in the
literature, hence, corresponds to the volume of human body fluids (liters),
expressed per kilogram of body weight.
This value is about the same as that determined using the experimental
monkey data.
The constant parameter kmet was determined from a best-fit to the blood
concentration-time profile of methanol in human volunteers exposed to 200
ppm of methanol vapors for 4 h, as determined by Osterloh et al. (1996).
The km value was determined by adjustment to the data of Sedivec et al.
(1981) on the urinary excretion time course curves of methanol in volunteers
during and following an 8-h inhalation exposure to 300 mg/m3 of methanol
vapors.
The experimental data of Sedivec et al. (1981) on the time evolution of
urinary methanol concentrations were converted to cumulative urinary
excretion of methanol (in µmol) by considering an average time-dependent
fraction of a daily urinary excretion of 1.5 l (Knuiman et al., 1986).
Model simulation.
Once the parameters were determined individually by statistical fits to the
experimental data, mathematical resolution of the complete model, as
represented by the system of differential equations, was performed by the
numerical Runge-Kutta method.
Model resolution and simulations were also conducted using Mathcad software.
This allows prediction of the time evolution of methanol and its metabolites
in the different model compartments.
In the model, the exposure dose was converted in µmoles for both the iv and
inhalation exposures.
Thus, whole body burdens and amounts excreted in urine and in the exhaled
air are first expressed in µmoles.
In order to simulate the blood concentrations of methanol or formate as a
function of time, the amounts in the whole body predicted by the model were
simply divided by the respective apparent volume of distribution.
For rats and monkeys, the apparent volume of distribution of formate (VdFA)
was estimated using a conservation of mass equation for formate burden, and
by a best-fit to the observed time course of experimental blood
concentration values of formate.
For monkeys, this amounts to 6 times the apparent volume of distribution of
methanol.
For humans, the same multiple was used.
To simulate the concentration-time profile of methanol in urine, predicted
excretion rates (dM(t)/dt = km x X(t), expressed in µmol/min) were divided
by the urinary flow rate (l/min).
To simulate the concentration-time profile of methanol in the exhaled air,
predicted exhalation rates (dE(t)/dt = kre x L(t) + kex x X(t), expressed in
µmol/min) were divided by the pulmonary ventilation rate (m3/min).
Simulations of exposure scenarios, where continuous or intermittent doses
are administered through time, were performed by introducing a nonhomogenous
term, g(t), describing these time varying inputs (see Appendix).
Simulations can also be conducted for different routes of exposure (iv,
inhalation).
Model Validation
The model developed using the previously mentioned data was validated using
a new set of experimental data.
This includes the kinetic time profiles presented in the inhalation studies
of Horton et al. (1992) in rats and monkeys and Batterman et al. (1998) in
human volunteers.
Also, some human data of Sedivec et al. (1981) not used in the development
of the model served to validate the model.
Validation using inhalation data of Horton et al. (1992) in rats.
The model developed using the iv data of Horton et al. (1992) in rats was
validated with the inhalation data of the same authors, on the blood
concentration-time profile of methanol during and following 6-h inhalation
exposures to 200, 1200, and 2000 ppm of methanol in male Fischer-344 rats (n
= 4 per group).
For those simulations, the average pulmonary ventilation rate used was 40
ml/min (equivalent to 0.0021 m3/h or 0.051 m3/day) for the 200 ppm dose, 40
ml/min (equivalent to 0.0024 m3/h or 0.058 m3/day) for the 1200 ppm dose,
and 60 ml/min (equivalent to 0.0033 m3/h or 0.080 m3/day) for the 2000 ppm
dose to obtain the best-fit to the experimental data as compared to the
average value of 3.04 l/h or 50 ml/min (equivalent to 0.0030 m3/h or 0.073
m3/day) reported by Horton et al. (1992).
Validation using inhalation data of Horton et al. (1992) in monkeys.
The model adapted to the monkey data of Dorman et al. (1996) was validated
using the data of Horton et al. (1992) on the blood concentration-time
profile of methanol in 3 young adult male rhesus monkeys (Macaca mulatta,
5-7 kg) exposed to methanol vapor concentrations of 200, 1200, or 2000 ppm
for 6 h.
For these simulations, the average pulmonary ventilation rate was that
reported by Horton et al. (1992), that is 48.9 l/h or 0.81 l/min (equivalent
to 0.049 m3/h or 1.2 m3/day).
Validation using inhalation data of Sedivec et al. (1981) and Batterman et
al. (1998) in humans.
The data of Sedivec et al. (1981) on the urinary excretion time course
curves of methanol in volunteers during and following 8-h inhalation
exposures to 102 and 205 mg/m3 of methanol vapors were used in the
validation process of the model for humans.
The model adapted to human data was also validated using the data of
Batterman et al. (1998) on the time-dependent disposition of methanol in
blood, urine, and breath of volunteers exposed to methanol vapor
concentration of 800 ppm for periods of 0.5, 1, and 2 h.
Batterman et al. (1998) presented their data as urinary and exhaled
concentration-time profiles (expressed in mg/l and ppm, respectively).
Although in this article the time courses of methanol cumulative excretion
in urine and exhaled air are usually presented to insure mass balance
conservation, it was also verified that the model gave a good prediction of
the overall concentration-time profiles of methanol in urine and exhaled air
(data not shown).
To obtain a good fit on both the concentration values and cumulative
burdens, a time-dependent fraction of a daily urinary excretion of 2.4 l for
the 30 min and 2 h exposures and of 2.7 l for the 1 h exposure had to be
considered.
It has been reported that the daily personal urine volume may commonly vary
from 0.6 l to more than 2.5 l (Knuiman et al., 1986).
The average pulmonary ventilation rate used was 11.3, 8.4, and 10.8 l/min
for the 30 min, 1 h, and 2 h exposures, respectively, to obtain a best-fit
to the exhalation data.
These latter rates are in the value range reported by Sedivec et al. (1981;
average [range]: 10.8 [8.4-13.8] l/min).
Model Developed Using the IV Data of Horton et al. (1992) in Male
Fischer-344 Rats
Table 2 presents the rat parameter values of the model determined using the
data of Horton et al. (1992) in male Fischer rats exposed via iv to 100 mg
of 14C-labeled methanol per kg of body weight (see Table 1 for the
description of symbols).
Figures 2 and 3 show that these parameter values allowed to reproduce
closely the data presented by Horton et al. (1992) on the time courses of
blood concentrations of methanol and formate as well as on the cumulative
urinary excretion of methanol and formate and the cumulative exhalation of
methanol and CO2.
View this table:
[in this window]
[in a new window]
TABLE 2 Numerical Values of Constant Parameters Used in the Model Adjusted
to Male Fischer-344 rat, Female Cynomolgus Monkey, and Human Data
View larger version (15K):
[in this window]
[in a new window]
FIG. 2. Model simulations (lines) compared with experimental data of Horton
et al. (1992) on the concentration-time courses of methanol (crossbars) and
formate (circles) in blood over 10 h following a single iv dose of 100 mg/kg
of 14C-labeled methanol in male Fischer-344 rats.
Each point represents mean value of experimental data (n = 4).
View larger version (15K):
[in this window]
[in a new window]
FIG. 3. (A) Model simulations (lines) compared with experimental data of
Horton
groups.yahoo.com/group/aspartameNM/messages
by Rich Murray
Monday, Jan. 03, 2005 at 8:25 PM
rmforall@comcast.net 505-986-9103 1943 Otowi Road, Santa Fe, New Mexico 87505
[ Continued ]
FIG. 3. (A) Model simulations (lines) compared with experimental data of
Horton et al. (1992) on the cumulative urinary excretion profiles of
methanol (crossbars) and formate (circles) over 18 h following a single iv
dose of 100 mg/kg of 14C-labeled methanol in male Fischer-344 rats.
Each point represents mean value of experimental data (n = 4).
(B) Model simulations (lines) compared with experimental data of Horton et
al. (1992) on the cumulative exhalation profiles of methanol (crossbars) and
CO2 (squares) over 18 h following a single iv dose of 100 mg/kg of
14C-labeled methanol in male Fischer-344 rats.
Each point represents mean value of experimental data (n = 4).
The estimated average Michaelis-Menten affinity constant value reported in
Table 2 and determined using the iv data (Km-IV of 770 µmol, which
represents the body burden of methanol corresponding to half of the maximal
velocity for methanol metabolism) shows that when injecting 100 mg/kg of
14C-methanol to Fischer rats (700 µmol), metabolism is not yet saturated.
From the product of Km-IV and kmet, an average Vmax value of 411 µmol/h can
be calculated.
The model predicts that methanol elimination from the whole body is quite
rapid (mean elimination half-life of 1.3 h) and that, on average, only 0.01%
of methanol remains in the unchanged form 18 h following iv injection of 100
mg/kg of 14C-methanol in rats.
Peak levels of free formaldehyde in the whole body are reached 0.5 h
postdosing, at which time formaldehyde burden represents on average 3.2% of
the injected dose.
Virtually no free formaldehyde remains in the body 18 h postexposure.
The metabolism of methanol to formaldehyde (kmet) is predicted to be the
rate limiting step in the whole body elimination kinetics of free
formaldehyde.
Indeed, the biotransformation of formaldehyde to its by-products is
estimated to be very rapid (kform + koth being very large) compared to
methanol metabolism to formaldehyde (kmet), as apparent when comparing
reports of McMartin et al. (1979) and Horton et al. (1992).
On the other hand, according to model predictions, peak levels of unbound
formate in the whole body are reached only 3-3.5 h postexposure where
average formate burden represents 20.1% of injected 14C-methanol.
Eighteen h postexposure, on average 0.5% of the dose remains in the body as
free formate.
Initial build-up of unbound formate in the body prior to attrition is
dependent on the fact that the metabolism rate constant of formaldehyde to
formate (kform) is very rapid (average half-life of about 10 min) compared
to the major elimination route of formate, the metabolism rate to CO2 and
subsequent exhalation (kCO2), for which a mean half-life of 2.2 h can be
calculated.
Since the urinary excretion of formate is negligible compared to CO2
exhalation, the former contributes only marginally to the whole body time
course of formate.
In fact, the model predicts that on average 48.8% of the 14C-methanol iv
dose is eliminated as exhaled CO2 as compared to 1.7% as urinary formate,
which is congruent with the experimental results of Horton et al. (1992).
In comparison, it is estimated from the model that on average 0.8% of the
dose is excreted as unchanged methanol in the urine and 2.4% of body
methanol is exhaled unchanged again in accordance with the experimental data
of Horton et al. (1992).
Model Validation Using the Inhalation Data of Horton et al. (1992) in
Fischer-344 Rats
With the parameter values determined using the iv data of Horton et al.
(1992), the model was applied to another set of data from the same authors
on the blood concentration-time profiles of methanol during and following
6-h inhalation exposures to 200, 1200, and 2000 ppm of methanol in male
Fischer-344 rats.
It gave a good prediction of the time-course curves for the 2 lowest doses
but underestimated the blood concentrations for the 2000 ppm dose (data not
shown).
Thus, a new value of the saturation constant Km was estimated from a
statistical best-fit on the blood concentration-time profile data of Horton
et al. (1992) in male Fischer-344 rats exposed by inhalation to 2000 ppm of
methanol vapors for 6 h (Km-Inh) (see Table 2).
This Km-Inh value was about 3 times smaller than that determined with the iv
data (on average 235 µmol).
Thus, after inhalation exposure to 2000 ppm, saturation of methanol
metabolism appears to occur at a lower body burden.
With this Km-Inh value, a Vmax of 125 µmol/h was calculated. Using this
newly determined Km constant for an inhalation exposure, the proposed model
provided a close approximation to the data of Horton et al. (1992) on the
blood concentration-time profiles of methanol in male Fischer-344 rats
exposed to vapor concentrations of 200, 1200, and 2000 ppm of methanol for 6
h (Fig. 4).
View larger version (18K):
[in this window]
[in a new window]
FIG. 4. Model simulations (lines) compared with experimental data of Horton
et al. (1992) on the time courses of methanol concentrations in blood during
and following 6-h inhalation exposures to 200 (diamonds), 1200 (crossbars),
and 2000 (squares) ppm of methanol vapors in male Fischer-344 rats.
Each point represents mean value of experimental data (n = 4).
Model Adapted to Female Cynomolgus Monkey Data of Dorman et al. (1994)
Using the conceptual and functional representation of the model established
with rat data, the model was adapted to monkeys by adjusting parameters
values (see Table 2), through a statistical best-fit, to the data of Dorman
et al. (1994) in female cynomolgus monkeys exposed by inhalation to methanol
vapors.
As observed in rats, pulmonary absorption of methanol was estimated to be
very rapid (a few minutes) as compared to the metabolism rate constant kmet
of whole body methanol to formaldehyde.
The predicted pulmonary absorption fraction of methanol in monkeys was in
the same range as that determined in rats.
The estimated monkey constant kmet was however 1.8 times higher than in
rats. Interestingly, contrary to the rat, according to the data of Dorman et
al. (1994), no saturation of methanol metabolism was apparent in monkeys
even after a 2-h inhalation exposure to 2000 ppm.
Further comparison of monkey and rat parameter values shows that the
estimated monkey metabolism rate constant kform of whole body formaldehyde
to formate was 2.0 times lower than that of rats.
This was also the case for exhalation rate constant kex of absorbed methanol
(1.8 times).
The monkey kCO2 value, which represents a combined metabolism rate constant
of whole body formate to CO2 and transfer rate constant of CO2 to the
exhaled air, was estimated to be 2.6 times higher than in rats.
As observed with the rat data of Horton et al. (1992), no saturation of
formaldehyde or formate metabolism was apparent from the data of Dorman et
al. (1994).
It is also noteworthy that the estimated monkey transfer rate constant ku of
whole body formate to urine was 5.4 times lower than in rats and the monkey
transfer rate constant km of whole body methanol to urine was 12.8 times
smaller than that obtained for rats.
The estimated monkey apparent volume of distribution of methanol and
formate, expressed in liters per kilogram of body weight, were only slightly
lower than those of the rats (1.2 and 1.4 times, respectively).
With the parameter values described in Table 2, Figure 5 shows that the
model provides a close approximation to the data obtained by Dorman et al.
(1994) on the blood concentration-time profiles of methanol and formate as
well as the time dependent variations in methanol and CO2 exhalation rates
over the 8-h period following the beginning of a 2-h inhalation exposure to
900 ppm of 14C-methanol in adult female cynomolgus monkeys.
Although the corresponding detailed urinary excretion profiles of methanol
and formate were not depicted by Dorman et al. (1994), cumulative excretion
of methanol and formate in urine was reported.
The model succeeded in reproducing closely these values (0.43 µmol predicted
as compared to 0.41 µmol observed on average for urinary methanol, and 1.12
µmol predicted as compared to 1.15 µmol observed on average for urinary
formate).
View larger version (16K):
[in this window]
[in a new window]
FIG. 5. (A) Model simulations (lines) compared with experimental data of
Dorman et al. (1994) on the time courses of methanol (crossbars) and formate
(circles) concentrations in blood during and following a 2-h inhalation
exposure to 900 ppm of 14C-methanol in adult female cynomolgus monkeys
(Macaca fascicularis). Each point represents mean value of experimental data
(n = 4). (B) Model simulations (lines) compared with experimental data of
Dorman et al. (1994) on the time courses of methanol (crossbars) and CO2
(squares) exhalation rates during and following a 2-h inhalation exposure to
900 ppm of 14C-methanol in adult female cynomolgus monkeys. Each point
represents mean value of experimental data (n = 4).
Model Validation Using the Inhalation Data of Male Rhesus Monkeys of Horton
et al. (1992)
The model, with parameter values adapted as above to cynomolgus monkey data
of Dorman et al. (1994), was further validated using experimental results of
Horton et al. (1992) in young male rhesus monkeys exposed for 6 h to vapor
concentrations of 1200 and 2000 ppm (These authors also exposed monkeys to
200 ppm but concentration values were too small to provide an accurate
prediction.)
It was assumed that differences in the kinetics were mainly a result of
interstrain differences in the metabolism rate of methanol, kmet.
With a smaller average kmet value of 0.22/h determined by statistical
best-fit for larger male rhesus monkeys (5-7 kg) as compared to 0.96/h for
smaller female cynomolgus monkeys (3.5-5 kg), the model was able to
reproduce the concentration-time course data of methanol in blood of Horton
et al. (1992) as seen in Figure 6.
View larger version (14K):
[in this window]
[in a new window]
FIG. 6. Model simulations (lines) compared with experimental data of Horton
et al. (1992) on the time courses of methanol concentrations in blood
following 6-h inhalation exposures to 1200 (crossbars) and 2000 (circles)
ppm of methanol vapors in young male rhesus monkeys (Macaca mulatta). Each
point represents mean value of experimental data (n = 3).
It is also interesting to note that, as reported by Horton et al. (1992),
the model predicts that blood formate concentrations in monkeys will not
exceed endogenous background values even for 6-h inhalation exposures to
2000 ppm of methanol vapors (data not shown).
This was also observed when simulating the data of Dorman et al. (1994) on
the blood concentration-time course curve of formate in monkeys exposed to
900 ppm of methanol vapors for 2 h.
Model Adapted to the Human Data of Osterloh et al. (1996) and Sedivec et al.
(1981)
The parameter values estimated by fitting the model to the observed data of
Osterloh et al. (1996) and Sedivec et al. (1981) on the disposition of
methanol and its metabolites in humans are presented in Table 2.
The estimated value of kmet was in the same range as that determined in
animals.
The km value was estimated to be close to that obtained in rats (1.5 times
lower) but 8.3 times higher than that of monkeys.
Figure 7 shows that the model simulates correctly the data obtained by
Osterloh et al. (1996) on the concentration-time course of blood methanol in
human volunteers exposed by inhalation to 200 ppm of methanol for 4 h.
The model included a constant background whole body methanol burden of 2133
µmol, which corresponds to the mean blood concentration of 1.5 mg/l of
methanol measured by Osterloh et al. (1996) in control subjects at the end
of an 8-h frequent blood sampling period.
In accordance with the experimental data of Osterloh et al. (1996), the
model predicts a log-linear elimination of blood methanol over the 4-h
sampling period following exposure (data not shown), indicating the absence
of saturation of methanol metabolism for the 4-h inhalation exposure at 200
ppm.
View larger version (15K):
[in this window]
[in a new window]
FIG. 7. Model simulations (solid lines) compared with experimental data of
Osterloh et al. (1996) on the blood concentration-time profile of methanol
in human volunteers during and following a 4-h inhalation exposure to 200
ppm of methanol vapors (crossbars).
Background blood methanol concentration values considered for model
simulations (dashed lines) and experimentally determined by Osterloh et al.
(1996) over the course of their experimental study (circles) are also
represented.
Symbols represent mean experimental values from 22 subjects.
Figure 8 compares model simulations to the time dependent cumulative
excretion of methanol in human volunteers during and following 8-h
inhalation exposures to 102, 205, and 300 mg/m3, as determined from the data
of Sedivec et al. (1981).
A mean background whole body burden of methanol of 700 to 1000 µmol
depending on the dose (equivalent to a blood concentration of 0.4-0.6 mg/l)
was included in the model, which gives predicted baseline urinary
concentrations in the same value range as those experimentally observed (0.7
mg/l on average). With these initial conditions, predictions were in close
agreement with the experimentally observed data.
View larger version (17K):
[in this window]
[in a new window]
FIG. 8. Model simulations (lines) compared with experimental data of Sedivec
et al. (1981) on the cumulative urinary excretion time-course of methanol in
human volunteers during and following 8-h inhalation exposures to 102
(diamonds), 205 (crossbars), and 300 (squares) mg/m3 of methanol.
Symbols represent mean experimental values from 4 subjects.
Model Validation Using the Inhalation Data of Batterman et al. (1998) in
Human Volunteers
The model adapted to humans was applied to the data of Batterman et al.
(1998) in human volunteers exposed to methanol vapor concentrations of 800
ppm for 30 min, 1 h, and 2 h.
All the parameter values were kept as determined with the previous human
data of Osterloh et al. (1996) and Sedivec et al. (1981) except for the
pulmonary retention.
Indeed, for a proper simulation of the experimental data, the average
pulmonary absorption fraction had to be 0.76, 0.82, and 0.81 for the 30 min,
1, and 2 h exposures, respectively, which is congruent with the mean value
of 0.79 reported by Batterman et al. (1998).
With these values, Figures 9-11 show that simulations were in close
agreement with the experimentally determined concentration-time profiles of
methanol in blood, as well as the time evolution of methanol cumulative
excretion in urine and in the exhaled air for the various exposure
scenarios.
A good fit was obtained even when neglecting background methanol in the
whole body. Regarding Figure 11, the exhalation rate is almost constant
during the exposure, which explains the plateau for the cumulative
exhalation.
View larger version (16K):
[in this window]
[in a new window]
FIG. 9. Comparison of model simulations (lines) with experimental data
(symbols represent mean values from 4 subjects) of Batterman et al. (1998)
on the blood concentration-time profiles of methanol in 3 groups of human
volunteers during and following inhalation exposures to 800 ppm of methanol
vapors for 30 min (A), 1 h (B), and 2 h (C).
View larger version (14K):
[in this window]
[in a new window]
FIG. 10. Comparison of model simulations (lines) with experimental data
(symbols represent mean values from 4 subjects) of Batterman et al. (1998)
on the cumulative urinary excretion time courses of methanol in 3 groups of
human volunteers during and following inhalation exposures to 800 ppm of
methanol vapors for 30 min (A), 1 h (B), and 2 h (C).
View larger version (15K):
[in this window]
[in a new window]
FIG. 11. Comparison of model simulations (lines) with experimental data
(symbols represent mean values from 4 subjects) of Batterman et al. (1998)
on the cumulative exhalation time courses of methanol in 3 groups of human
volunteers during and following inhalation exposures to 800 ppm of methanol
vapors for 30 min (A), 1 h (B), and 2 h (C).
Prediction of the Time Course Curves of Methanol and Formate Concentrations
in Blood and Urine during a 5-Day Continuous Exposure to Methanol Vapor
Concentrations of 200 ppm in Humans
The model can also be used to predict the time-dependent variations of
methanol and formate concentrations in human blood and urine during a
continuous inhalation exposure to 200 ppm of methanol, considering a
negligible background burden of methanol, an absorption fraction of 0.577, a
pulmonary ventilation rate of 10.8 l/min, and a daily urinary excretion rate
of 1.5 l.
Near steady state levels were reached within 20 h following the start of
exposure.
At the end of a 5-day exposure period, predicted blood concentration of
methanol was 5.5 mg/l (171 µmol/l) and that of formate was 0.16 mg/l (3.5
µmol/l).
The latter formate concentration was obtained by considering an apparent
volume of distribution of formate in humans (in l/kg of body weight) similar
to that calculated for monkeys.
With this exposure level, the model predicts near steady state urinary
concentrations of methanol of 8.1 mg/l (252 µmol/l) and of formic acid of
1.5 mg/l (31.7 µmol/l, 0.97 mg/g creatinine, or 2390 µmol/mol creatinine).
Thus, at the end of a 5-day continuous inhalation exposure to 200 ppm of
methanol vapors, predicted methanol concentrations in blood and urine were 5
to 11 times greater than reported mean background values of unexposed
subjects (1 mg/l in blood and 0.73 mg/l in urine) (Osterloh et al., 1996;
Sedivec et al., 1981).
On the other hand, predicted concentrations of blood formate and urinary
formic acid in humans (0.16 and 1.5 mg/l, respectively), although in
accordance with the experimental data from methanol exposures in primates
and humans, were well below mean background values of unexposed subjects
(4.9-10.3 mg/l in blood and 6.3-13 mg/l in urine) reported by various
authors (Baumann and Angerer, 1979; D'Alessandro et al., 1994; Heinrich and
Angerer, 1982; Lee et al., 1992; Osterloh et al., 1996).
The model simulations suggest that an 8-h inhalation exposure of at least
500 to 2000 ppm, without physical activities, would be necessary for blood
formate and urinary formic acid concentrations to reach reported mean
background values.
The exact exposure levels necessary depend on the values assumed for the
absorption fraction, the pulmonary ventilation rate, and the daily urinary
excretion rate.
There are considerable variations in the literature for these parameters.
Model Description of the Kinetics of Methanol and Its Metabolites
A biologically based dynamic model was developed to simulate the uptake and
disposition of methanol and its metabolites (formaldehyde, formate, CO2) in
animals and humans.
Based on the in vivo time profiles of methanol, formate, and CO2 in blood
and accessible biological matrices, the model was able to reproduce the
essential kinetic processes of methanol disposition.
It can now be used to quantitatively relate the parent compound or the
metabolites in biological matrices to the absorbed dose and tissue burdens
at any point in time in rats, monkeys, and humans for different exposure
situations, thus reducing the uncertainties in the dose-response
relationship, animal-to-human, and exposure scenario comparisons.
The model showed that the kinetics of systemic methanol were dependent on
the pulmonary uptake and on the metabolism of methanol to formaldehyde. The
pulmonary absorption fraction and ventilation rate were the only model
parameters that needed to be modified within a species to provide a good
prediction of all the data sets.
These predicted parameters were, however, in the value range reported in the
published literature (Dorman et al., 1994; Fisher et al., 2000; Horton et
al., 1992; Sedivec et al., 1981).
The pulmonary absorption fraction did not appear to be influenced by the
exposure level or duration nor by the pulmonary ventilation rate, as
observed previously by Sedivec et al. (1981) and Medinsky et al. (1997).
For all the other parameters, a single set of values for a given species and
strain was found to provide a close approximation to the available kinetic
time profile data.
In particular, a single average value for the metabolism rate constants can
be used in the model for a given exposure route.
In accordance with the published animal data (Dorman et al., 1994; Horton et
al., 1992), the model predicts that absorbed methanol is eliminated mainly
by metabolism to formaldehyde and that only a minor fraction of the exposure
dose is eliminated as unchanged methanol in urine.
On the other hand, from the rat data of Horton et al. (1992), differences in
the saturation of methanol metabolism were observed depending on the
exposure route.
Indeed, in the rat model, a same value for the metabolism rate constant of
whole body methanol to formaldehyde, kmet, was found to provide a close
approximation to the data of Horton et al. (1992) on the blood
concentration-time profiles of methanol after iv and inhalation exposures to
methanol in Fischer-344 rats.
However, the Km value determined using the inhalation data was 3 times
smaller than that obtained using the iv data.
Although methanol has been reported to be metabolized mainly in the liver,
pulmonary metabolism is also likely to occur.
Indeed, the catalase-peroxidase system responsible for a major fraction of
methanol metabolism in rats is widely distributed in mammalian tissues
(Housset, 1986; Morikawa and Harada, 1969; Sugata et al., 1979).
It is, in particular, present in the membranes of the upper respiratory
tract, the main site of pulmonary absorption of methanol (Perkins et al.,
1996).
Of course, given that the Km parameters were estimated from mean blood
concentration data without taking into account interindividual variations,
it cannot be excluded that there is no significant difference between the 2
route-specific Km values.
It should be remembered that, only in the case of methanol metabolism to
formaldehyde was a saturation constant necessary.
As mentioned previously, for the exposure dose range of the studies on which
the model is based, no saturation of formate or CO2 metabolism was apparent
(Dorman et al., 1994; Horton et al., 1992; Osterloh et al., 1996; Sedivec et
al., 1981).
Though the saturation of formate metabolism has been reported after very
high iv doses of sodium formate in rats (164, 328, and 492 mg/kg; Damian and
Raabe, 1996) and appeared to occur in a case of methanol poisoning in a
human subject (Jacobsen et al., 1988), under inhalation exposures levels in
occupational and general environments, it is unlikely to occur.
According to model predictions, congruent with the data in the literature
(Dorman et al., 1994; Horton et al., 1992), a certain fraction of
formaldehyde is readily oxidized to formate, a major fraction of which is
rapidly converted to CO2 and exhaled, whereas a small fraction is excreted
as formic acid in urine.
However, fits to the available data in rats and monkeys of Horton et al.
(1992) and Dorman et al. (1994) show that, once formed, a substantial
fraction of formaldehyde is converted to unobserved forms.
This pathway contributes to a long-term unobserved compartment.
The latter, most plausibly, represents either the formaldehyde that
(directly or after oxidation to formate) binds to various endogenous
molecules (Heck et al., 1983; Røe, 1982)
or is incorporated in the tetrahydrofolic-acid-dependent one-carbon pathway
to become the building block of a number of synthetic pathways (Røe, 1982;
Tephly and McMartin, 1984).
That substantial amounts of methanol metabolites or by-products are retained
for a long time is verified by Horton et al. (1992) who estimated that 18 h
following an iv injection of 100 mg/kg of 14C-methanol in male Fischer-344
rats, only 57% of the dose was eliminated from the body.
From the data of Dorman et al. (1994) and Medinsky et al. (1997), it can
further be calculated that 48 h following the start of a 2-h inhalation
exposure to 900 ppm of 14C-methanol vapors in female cynomolgus monkeys,
only 23% of the absorbed 14C-methanol was eliminated from the body.
These findings are corroborated by the data of Heck et al. (1983) showing
that 40% of a 14C-formaldehyde inhalation dose remained in the body 70 h
postexposure.
In the present study, the model proposed rests on acute exposure data, where
the time profiles of methanol and its metabolites were determined only over
short time periods (a maximum of 6 h of exposure and a maximum of 48 h
postexposure).
This does not allow observation of the slow release from the long-term
components.
It is to be noted that most of the published studies on the detailed
disposition kinetics of methanol regard controlled short-term (iv injection
or continuous inhalation exposure over a few hours) methanol exposures in
rats, primates, and humans (Batterman et al., 1998; Damian and Raabe, 1996;
Dorman et al., 1994; Ferry et al., 1980; Fisher et al., 2000; Franzblau et
al., 1995; Horton et al., 1992; Jacobsen et al., 1988; Osterloh et al.,
1996; Pollack et al., 1993; Sedivec et al., 1981; Ward et al., 1995; Ward
and Pollack, 1996).
Experimental studies on the detailed time profiles following controlled
repeated exposures to methanol are lacking.
Data on methanol and formate concentrations in spot blood and urine samples
of chronically exposed workers (Baumann and Angerer, 1979; Kawai et al.,
1991; Yasugi et al., 1992) are available but uncertainties regarding the
exposure dose and concomitant exposure to other chemicals limit their use in
the elaboration of a kinetic model.
With regard to the apparent volume of distribution of methanol, which was
calculated in the current study using classic approaches (see Method and
Model Presentation), it was expected that its value would correspond
approximately to the whole body water content.
The slightly larger weight adjusted volume of distribution of methanol
calculated in rats (0.92 l/kg of body weight) as compared to monkeys (0.77
l/kg of body weight) can be explained by the smaller adipose tissue fraction
of body weight in rats.
As for the apparent volume of distribution of formate determined in this
study, the weight adjusted values calculated in rats and monkeys were in the
same range, although slightly higher in rats than in monkeys (6.4 and 4.6
l/kg of body weight, respectively).
However, the volume of distribution of formate was larger than that of
methanol, which strongly suggests that formate distributes in body
constituents other than water, such as proteins.
The closeness of our simulations to the available experimental data on the
time course of formate blood concentrations is consistent with the volume of
distribution concept (i.e., rapid exchanges between the nonblood pool of
formate and blood formate).
Species Differences in the Kinetics of Methanol and Its Metabolites
Critical biological determinants of species differences in the disposition
of methanol and its metabolites were determined from in vivo data from
several studies (Batterman et al., 1998; Fisher et al., 2000; Horton et al.,
1992; Sedivec et al., 1981).
In agreement with their findings, the model predicts that the average
pulmonary absorption fraction fabs of methanol and the metabolism rate
constant kmet of whole body methanol to formaldehyde were in the same value
range in rats, monkeys, and humans (on average 0.58-0.82 for fabs and
0.219-0.96/h for kmet).
However, the saturation of methanol metabolism appeared to occur at a lower
exposure dose in rats than in monkeys and humans.
Indeed, from the data of Horton et al. (1992) on the blood
concentration-time profile of methanol in rats exposed to 2000 ppm of
methanol vapors for 6 h, a Km value of 36.6 mg/l of blood and Vmax of 19.4
mg/l/h were estimated in the current study whereas following a similar
exposure in monkeys, no saturation of methanol metabolism was apparent.
The model also predicts that there is no saturation of methanol metabolism
from the data of Batterman et al. (1998) in human volunteers exposed to 800
ppm of methanol vapors for 2 h nor from those of Sedivec et al. (1981) in
volunteers exposed to 229 ppm of methanol vapors for 8 h.
Interestingly, a striking species difference in the kinetics was attributed
to a metabolism rate constant ratio kform/kfald of whole body formaldehyde
to formate twice as high in rats than in monkeys (0.53 vs. 0.26).
Thus, in monkeys and plausibly humans, a much larger fraction of body
formaldehyde is rapidly converted to unobserved forms rather than passed on
to formate and eventually CO2.
Comparison of the Current Model with Others Previously Published
The current biologically based dynamic model can be compared to some of the
previously published models.
In particular, Horton et al. (1992) developed a PBPK model to describe the
kinetics of methanol and its metabolites in rats, monkeys, and humans.
Their model was comprised of 4 compartments: liver, kidney, and richly and
slowly perfused tissues.
As in our model, the metabolism of methanol to formaldehyde was assumed to
be the main biological determinant of methanol elimination kinetics.
In addition, in both the current model and that published by Horton et al.
(1992), not only were the kinetics of methanol in blood, urine, and exhaled
air modeled but also the time evolution of formate in blood and urine and of
CO2 in the exhaled air.
However, in the study of Horton et al. (1992), 2 saturable metabolic
pathways for methanol metabolism were considered whereas in our study, even
by introducing only 1 metabolism route for methanol, with saturable
elimination, the model gave a good prediction of the experimental data.
In the PBPK model of Horton et al. (1992), the metabolism of formate and CO2
was also assumed to follow Michaelis Menten kinetics.
In our model, as mentioned previously, no saturation constants for these
metabolism processes were introduced since fits to the available time course
data suggested the absence of saturation of formate and CO2 metabolism in
the exposure dose range used in the studies on which the model is based.
Furthermore, conceptual and functional differences between the current model
and the PBPK model of Horton et al. (1992) are related to the fact that the
current model compartmentalization is dependent on the availability of
experimental data on the detailed time course of methanol and its
metabolites in blood, tissues, and excreta and on the hierarchy of the time
scales for the various biological processes.
The main structural difference between our model and that of Horton et al.
(1992) concerns our regrouping into a single compartment the methanol body
burden whereas Horton et al. (1992) have fragmented the body into several
compartments according to the general PBPK structure.
In our model, methanol body burden regrouping relies on the fact that
methanol distributes uniformly and rapidly in total body water and thus the
apparent volume of distribution of methanol corresponds to the total body
water content. This allowed us to reduce the number of parameters to be
determined to describe the overall model dynamics of methanol.
Based on the available data on methanol blood kinetics for the 3 species
studied, this regrouping also enabled the determination of species specific
parameters by direct fits, without the need for allometric extrapolation.
Furthermore, the current model ensures conservation of mass by the
introduction of an unobserved metabolite compartment.
In the model of Horton et al. (1992), to account for the fraction of the
methanol dose that was unobserved experimentally and thus to obtain a good
fit to their experimental data on the cumulative exhalation of CO2 in rats
exposed to 14C-labeled methanol, the rate of formate metabolism had to be
multiplied by 0.6 to correspond to the fraction of the methanol dose
eventually excreted as CO2 over the 18-h sample collection period of their
study.
More recently, Fisher et al. (2000) published a PBPK model for monkeys to
describe the kinetics of methanol.
The structure of their PBPK model for methanol was similar to that of Horton
et al. (1992) but also accounted for the fractional systemic uptake of
inhaled methanol vapors in the lungs.
This fractional systemic uptake was also introduced in our model.
Prediction of the Most Useful Biological Indicator of Exposure to Methanol
The biological monitoring of exposure, through the analysis of blood
concentrations or urinary and exhaled levels, has become an increasingly
popular means of estimating the absorbed dose.
This model can be used in conjunction with biological measurements of
methanol and formate or formic acid to determine the level of exposure and
subsequent build-up in tissues.
It can also help to establish the best biomarker of exposure, the sampling
strategy for routine monitoring and the significance of measurements at
different times.
Since systemic formate is thought to be responsible for a large part of the
deleterious effects induced by methanol exposures (Tephly and McMartin,
1984), the measurement of blood formate or urinary formic acid appears
interesting a priori for the biological monitoring of exposure to methanol.
However, the model shows that background concentrations of formate are much
higher than those stemming from fairly high methanol exposures.
Indeed, the model, adapted to kinetic data in human volunteers exposed
acutely to methanol vapors, predicts that 8-h inhalation exposures ranging
from 500 to 2000 ppm are needed to increase blood formate concentrations
above reported mean endogenous values of 4.9 to 10.3 mg/l (Baumann and
Angerer, 1979;
Lee et al., 1992; Osterloh et al., 1996), and for urinary formic acid
concentrations to reach the published mean background values of 6.3 to 13
mg/l (Baumann and Angerer, 1979; D'Alessandro et al., 1994; Heinrich and
Angerer, 1982).
The monkey data of Dorman et al. (1994) show that even after a 2-h
inhalation exposure to 900 ppm of 14C-methanol in female cynomolgus monkeys,
14C-formate concentrations in blood were far below normal endogenous values.
Likewise, studies in human volunteers acutely exposed to methanol, at the
level of 200 ppm, concur to indicate that blood formate and urinary formic
acid concentrations remain within the background value range of unexposed
subjects (D'Alessandro et al., 1994; Franzblau et al., 1993; Lee et al.,
1992; Osterloh et al., 1996).
Only in the studies of Kawai et al. (1991) and Yasugi et al. (1992) was a
significant correlation between the urinary excretion of formic acid and
exposure to methanol vapors observed.
However, the workers were exposed to airborne concentrations of methanol of
up to 4000 ppm over an 8-h workshift.
These findings suggest that it is not justified to monitor concentrations of
blood formate or urinary formic acid at methanol exposure levels in the
range of or below the airborne threshold limit value of 200 ppm for
occupational settings.
If toxic effects do occur following low level methanol exposures, the mode
of action is not likely to be through the accumulation of formate.
As suggested by some reports (Cook et al., 1991; Kingsley and Hirsch, 1954),
it may rather be attributable to methanol itself.
The use of formate as a biomarker of exposure to methanol is further limited
by the fact that it is not a specific metabolite of methanol exposure.
Also, background concentrations of formate are subject to wide
interindividual variations (Baumann and Angerer, 1979; D'Alessandro et al.,
1994; Franzblau et al., 1995; Heinrich and Angerer, 1982; Lee et al., 1992;
Osterloh et al., 1996; Sedivec et al., 1981).
This leaves blood and urinary methanol as the most appropriate biomarkers of
absorbed methanol.
Since the model relates blood and urinary methanol burdens to the exposure
dose and body burdens of metabolites at all time points, it can be of great
use in reconstructing past and present exposure levels starting from
methanol amounts in blood and urine.
Methanol Kinetics: First Order Linear Differential Equations for Each
Compartment
Kinetics of the Methanol Form
From Figure 1, the following differential equations are obtained (see Table
1 for definitions of symbols):
((1))
where g(t) is the pulmonary exposure dose per unit of time. g(t) = Cexp x VR
where Cexp is the exposure concentration and VR is the pulmonary ventilation
rate. For an iv injection, g(t) = 0 for t > 0 and at time t = 0, X(0) = 100%
of dose.
The fraction of absorption through the lungs can be defined as fabs =
kabs/(kabs + kre).
((2))
where
Considering the rapid exchange rates between the various internal organs and
blood, and thus between the whole body burden and blood, it can be
considered that
((3))
where B(t) is the blood concentration of methanol as a function of time.
((4))
((5))
Kinetics of the Formaldehyde Form
((6))
The global breakdown rate of formaldehyde, kfald = kform + koth, is very
large compared to the subsequent transfer rates {ku and kCO2} because
observed formaldehyde levels are very small compared to formate levels.
This implies rapid breakdown of formaldehyde compared to formate elimination
rates.
The rate of formaldehyde breakdown, kfald, was given the value reported by
McMartin et al. (1979) in cynomolgus monkeys, corresponding to a half-life
of 1.5 min. However, its exact value is not relevant to the model's
unfolding, only the ratios kform/kfald and koth/kfald are.
Kinetics of the Other Forms
((7))
((8))
((9))
Kinetics of the Formate Form
((10))
((11))
((12))
Mass Balance Verification
Batterman, S. A., Franzblau, A., D'Arcy, J. B., Sargent, N. E., Gross, K.
B., and Schreck, R. M. (1998). Breath, urine, and blood measurements as
biological exposure indices of short-term inhalation exposure to methanol.
Int. Arch. Occup. Environ. Health 71, 325-335.[Medline]
Baumann, K., and Angerer, J. (1979). Occupational chronic exposure to
organic solvents. VI. Formic acid concentration in blood and urine as an
indicator of methanol exposure. Int. Arch. Occup. Environ. Health 42,
241-249.[Medline]
Bolon, B., Dorman, D. C., Janszen, D., Morgan, K. T., and Welsch, F. (1993).
Phase-specific developmental toxicity in mice following maternal methanol
inhalation. Fundam. Appl. Toxicol. 21, 508-516.[Medline]
Carrier, G., Bouchard, M., Brunet, R. C., and Caza, M. (2001a). A
toxicokinetic model for predicting the tissue distribution and elimination
of organic and inorganic mercury following exposure to methyl mercury in
animals and humans. II. Application and validation of the model in humans.
Toxicol. Appl. Pharmacol. 171, 50-60.[Medline]
Carrier, G., and Brunet, R. C. (1999). A toxicokinetic model to assess the
risk of azinphosmethyl exposure in humans through measures of urinary
elimination of alkylphosphates. Toxicol. Sci. 47, 23-32.[Abstract]
Carrier, G., Brunet, R. C., and Brodeur, J. (1995a). Modeling of the
toxicokinetics of polychlorinated dibenzo-p-dioxins and dibenzofurans in
mammalians, including humans. I. Nonlinear distribution of PCDD/PCDF body
burden between liver and adipose tissues. Toxicol. Appl. Pharmacol. 131,
253-266.[Medline]
Carrier, G., Brunet, R. C., and Brodeur, J. (1995b). Modeling of the
toxicokinetics of polychlorinated dibenzo-p-dioxins and dibenzofurans in
mammalians, including humans. II. Kinetics of absorption and disposition of
PCDDs/PCDFs. Toxicol. Appl. Pharmacol. 131, 267-276.[Medline]
Carrier, G., Brunet, R. C., Caza, M., and Bouchard, M. (2001b). A
toxicokinetic model for predicting the tissue distribution and elimination
of organic and inorganic mercury following exposure to methyl mercury in
animals and humans. I. Development and validation of the model using
experimental data in rats. Toxicol. Appl. Pharmacol. 171, 38-49.[Medline]
Cook, M. R., Bergman, F. J., Cohen, H. D., Gerkovich, M. M., Graham, C.,
Harris, R. K., and Siemann, L. G. (1991). Effects of Methanol Vapor on Human
Neurobehavioral Measures. Research Report Number 42. Health Effects
Institute, Cambridge, MA.
D'Alessandro, A., Osterloh, J. D., Chuwers, P., Quinlan, P. J., Kelly, T.
J., and Becker, C. E. (1994). Formate in serum and urine after controlled
methanol exposure at the threshold limit value. Environ. Health Perspect.
102, 178-181.[Medline]
Damian, P., and Raabe, O. G. (1996). Toxicokinetic modeling of
dose-dependent formate elimination in rats: In vivo-in vitro correlations
using the perfused rat liver. Toxicol. Appl. Pharmacol. 139, 22-32.[Medline]
Dorman, D. C., Moss, O. R., Farris, G. M., Janszen, D., Bond, J. A., and
Medinsky, M. A. (1994). Pharmacokinetics of inhaled [14C]methanol and
methanol-derived [14C]formate in normal and folate-deficient cynomolgus
monkeys. Toxicol. Appl. Pharmacol. 128, 229-238.[Medline]
Downie, A., Khattab, T. M., Malik, M. I. A., and Samara, I. N. (1992). A
case of percutaneous industrial methanol toxicity. Occup. Med. 42,
47-49.[Abstract]
Ferry, D. G., Temple, W. A., and McQueen, E. G. (1980). Methanol monitoring.
Comparison of urinary methanol concentration with formic acid excretion rate
as a measure of occupational exposure. Int. Arch. Occup. Environ. Health 47,
155-163.[Medline]
Fisher, J. W., Dorman, D. C., Medinsky, M. A., Welsch, F., and Conolly, R.
B. (2000). Analysis of respiratory exchange of methanol in the lung of the
monkey using a physiological model. Toxicol. Sci. 53, 185-193.[Abstract/Free
Full Text]
Franzblau, A., Batterman, S. A., D'Arcy, J. B., Sargent, N. E., Gross, K.
B., and Schreck, R. M. (1995). Breath monitoring of inhalation and dermal
methanol exposure. Appl. Occup. Environ. Hyg. 10, 833-839.
Franzblau, A., Lee, E. W., Schreck, R. M., D'Arcy, J. B., Santrock, J., and
Levine, S. P. (1993). Absence of formic acid accumulation in urine following
five days of methanol exposure. Appl. Occup. Environ. Hyg. 8, 883-888.
Goodman, J. I., and Tephly, T. R. (1968). The role of hepatic microbody and
soluble oxidases in the peroxidation of methanol in the rat and monkey. Mol.
Pharmacol. 4, 492-501.[Abstract]
Health Effects Institute (1987). Automotive Methanol Vapors and Human
Health: An Evaluation of Existing Scientific Information and Issues for
Future Research (a Special Report). Health Effects Institute, Cambridge, MA.
Heck, H. A., Chin, T. Y., and Schmitz, M. C. (1983). Distribution of [14C]
formaldehyde in rats after inhalation exposure. In Formaldehyde Toxicity (J.
E. Gibson, Ed.), pp. 26-37. Hemisphere Publishing Corporation, Washington,
DC.
Heinrich, R., and Angerer, J. (1982). Occupational chronic exposure to
organic solvents. X. Biological monitoring parameters for methanol exposure.
Int. Arch. Occup. Environ. Health 50, 341-349.[Medline]
Horton, V. L., Higuchi, M. A., and Rickert, D. E. (1992). Physiologically
based pharmacokinetic model for methanol in rats, monkeys, and humans.
Toxicol. Appl. Pharmacol. 117, 26-36.[Medline]
Housset, B. (1986). Mechanisms of oxygen-induced lung injury. Arch. Int.
Physiol. Biochim. 94, S1-5.
IPCS (1997). Environmental Health Criteria 196-Methanol. International
Programme on Chemical Safety, World Health Organization, Geneva.
Jacobsen, D., Webb, R., Collins, T. D., and McMartin K. E. (1988). Methanol
and formate kinetics in late diagnosed methanol intoxication. Med. Toxicol.
Adverse Drug Exp. 3, 418-423.[Medline]
Kavet, S., and Nauss, K. M. (1990). The toxicity of inhaled methanol vapors.
Crit. Rev. Toxicol. 21, 21-50.[Medline]
Kawai, T., Yasugi, T., Mizunuma, K., Horiguchi, S., Hirase, Y., Uchida, Y.,
and Ikeda, M. (1991). Methanol in urine as a biological indicator of
occupational exposure to methanol vapor. Int. Arch. Occup. Environ. Health
63, 311-318.[Medline]
Kingsley, W. H., and Hirsch, F. G. (1954). Toxicologic considerations in
direct process spirit duplicating machines. Comp. Med. 6, 7-8.
Knuiman, J. T., Hautvast, A. J., van der Heyden, L., Geboers, J., Joossens,
J. V., Tornquist, H., Isaksson, B., Pietinen, P., Tuomilehto, U., Poulsen,
L., Flynn, A., Shortt, C., Böing, H., Yomtov, B., Magalhaes, E., Angelico,
F., Stefanutti, C., Fazio, C., Cantini, R., Ricci, G., Trichopoulou, A., and
Katapoti, J. (1986). A multi-centre study on completeness of urine
collection in 11 European centres. I. Some problems with the use of
creatinine and 4-aminobenzoic acid as marker of the completeness of
collection. Human Nutr. Clin. Nutr. 40, 229-237.
Lee, E. W., Terzo, T. S., D'Arcy, J. B., Gross, K. B., and Schreck, R. M.
(1992). Lack of blood formate accumulation in humans following exposure to
methanol vapor at the current permissible exposure limit of 200 ppm. Am.
Ind. Hyg. Assoc. J. 53, 99-104.[Medline]
Liesivuori, J., and Savolainen, H. (1991). Methanol and formic acid
toxicity: Biochemical mechanisms. Pharmacol. Toxicol. 69, 157-163.[Medline]
McMartin, K. E., Martin-Amat, G., Makar, A. B., and Tephly, T. R. (1977).
Methanol poisoning. V. Role of formate metabolism in the monkey. J.
Pharmacol. Exp. Ther. 201, 564-572.[Medline]
McMartin, K. E., Martin-Amat, G., Noker, P. E., and Tephly, T. R. (1979).
Lack of role for formaldehyde in methanol poisoning in the monkey. Biochem.
Pharmacol. 28, 645-649.[Medline]
Medinsky, M. A., Dorman, D. C., Bond, J. A., Moss, O. R., Janszen, D. B.,
and Everitt, J. I. (1997). Pharmacokinetics of methanol and formate in
female cynomolgus monkeys exposed to methanol vapors. Res. Rep. Health Eff.
Inst. 77,1-30; discussion 31-38.[Medline]
Morikawa, S., and Harada, T. (1969). Immunohistochemical localization of
catalase in mammalian tissues. J. Histochem. Cytochem. 17, 30-5.[Medline]
Nelson, B. K., Brightwell, S., MacKenzie, D. R., Khan, A., Burg, J. R.,
Weigel, W. W., and Goad, P. T. (1985). Teratological assessment of methanol
and ethanol at high inhalation levels in rats. Fundam. Appl. Toxicol. 5,
727-736.[Medline]
Nihlén, A., and Droz, P.-O. (2000). Toxicokinetic modelling of methyl
formate exposure and implications for biological monitoring. Int. Arch.
Occup. Environ. Health 73, 479-487.[Medline]
Osterloh, J. D., D'Alessandro, A., Chuwers, P., Mogadeddi, H., and Kelly, T.
J. (1996). Serum concentrations of methanol after inhalation at 200 ppm. J.
Occup. Environ. Med. 38, 571-576.[Medline]
Palese, M., and Tephly, T. R. (1975). Metabolism of formate in the rat. J.
Toxicol. Environ. Health 1, 13-24.[Medline]
Perkins, R. A., Ward, K. W., and Pollack, G. M. (1995). A pharmacokinetic
model of inhaled methanol in humans and comparison to methanol disposition
in mice and rats. Environ. Health Perspect. 103, 726-733.[Medline]
Perkins, R. A., Ward, K. W., and Pollack, G. M. (1996). Methanol inhalation:
Site and other factors influencing absorption, and an inhalation
toxicokinetic model for the rat. Pharm. Res. 13, 749-55.[Medline]
Pollack, G. M., and Brouwer, K. L. (1996). Maternal-fetal pharmacokinetics
of methanol. Res. Rep. Health Eff. Inst. 74,1-48; discussion 49-53.[Medline]
Pollack, G. M., Brouwer, K. L., and Kawagoe, J. L. (1993). Toxicokinetics of
intravenous methanol in the female rat. Fundam. Appl. Toxicol. 21,
105-110.[Medline]
Røe, O. (1982). Species differences in methanol poisonings. Crit. Rev.
Toxicol. 10, 275-286.[Medline]
Sedivec, V., Mraz, M., and Flek, J. (1981). Biological monitoring of persons
exposed to methanol vapours. Int. Arch. Occup. Environ. Health 48,
257-271.[Medline]
Sejersted, O. M., Jacobsen, D., Ovrebo, S., and Jansen, H. (1983). Formate
concentrations in plasma from patients poisoned with methanol. Acta Med.
Scand. 213, 105-110.[Medline]
Sugata, Y., Halbach, S., Allen, J., and Clarkson, T. W. (1979). Tissue
distribution of inhaled mercury vapor in acatalasemic mice. J. Environ. Sci.
Health C 13, 97-106.[Medline]
Tephly, T. R., and McMartin, K. E. (1984). Methanol metabolism and toxicity.
In Aspartame. Physiology and Biochemistry (L. D. Stegink and L. J. Filer,
Jr., Eds.), pp. 111-140. Marcel Dekker, New York.
U.S. DHHS (1993). Methanol toxicity. Agency for Toxic Substances and Disease
Registry. Am. Fam. Physician 47, 163-171.[Medline]
Ward, K. W., Blumenthal, G. M., Welsch, F., and Pollack, G. M. (1997).
Development of a physiologically based pharmacokinetic model to describe the
disposition of methanol in pregnant rats and mice. Toxicol. Appl. Pharmacol.
145, 311-322.[Medline]
Ward, K. W., Perkins, R. A., Kawagoe, J. L., and Pollack, G. M. (1995).
Comparative toxicokinetics of methanol in the female mouse and rat. Fundam.
Appl. Toxicol. 26, 258-264.[Medline]
Ward, K. W., and Pollack, G. M. (1996). Comparative toxicokinetics of
methanol in pregnant and nonpregnant rodents. Drug. Metab. Dispos. 24,
1062-1070.[Abstract]
Yasugi, T., Kawai, T., Mizunuma, K., Horiguchi, S., Iwami, O., Iguchi, H.,
and Ikeda, M. (1992). Formic acid excretion in comparison with methanol
excretion in urine of workers occupationally exposed to methanol. Int. Arch.
Occup. Environ. Health 64, 329-37.[Medline]
**************************************************************
Gosselin NH, Brunet RC, Carrier G.
Comparative occupational exposures to formaldehyde released from inhaled
wood product dusts versus that in vapor form.
Appl Occup Environ Hyg. 2003 May; 18(5): 384-93. PMID: 12746082
Bouchard M, Gosselin NH, Brunet RC, Samuel O, Dumoulin MJ, Carrier G.
Michèle Bouchard, Nathalie H. Gosselin, Robert C. Brunet, Onil Samuel,
Marie-Josée Dumoulin, and Gaétan Carrier
A toxicokinetic model of malathion and its metabolites as a tool to assess
human exposure and risk through measurements of urinary biomarkers.
Toxicol Sci. 2003 May; 73(1): 182-94. Epub 2003 Mar 25. Erratum in: Toxicol
Sci. 2003 Aug; 74(2): following table of contents. PMID: 12657741
Carrier G, Bouchard M, Brunet RC, Caza M.
A toxicokinetic model for predicting the tissue distribution and elimination
of organic and inorganic mercury following exposure to methyl mercury in
animals and humans. II. Application and validation of the model in humans.
Toxicol Appl Pharmacol. 2001 Feb 15;171(1):50-60. PMID: 11181111
Carrier G, Brunet RC, Caza M, Bouchard M.
A toxicokinetic model for predicting the tissue distribution and elimination
of organic and inorganic mercury following exposure to methyl mercury in
animals and humans. I. Development and validation of the model using
experimental data in rats.
Toxicol Appl Pharmacol. 2001 Feb 15;171(1):38-49. PMID: 11181110
**************************************************************
http://groups.yahoo.com/group/aspartameNM/message/1100
research on aspartame (methanol, formaldehyde, formic acid) toxicity:
Murray 2004.08.02 rmforall [ 2004.11.16 additions ]
Rich Murray, MA Room For All rmforall@comcast.net
1943 Otowi Road, Santa Fe, New Mexico 87505 USA 505-501-2298
http://groups.yahoo.com/group/aspartameNM/messages
137 members, 1,142 posts in a public searchable archive
The moderated newsgroup, bionet.toxicology , has accepted 25 of my long
reviews since March 24:
Dr. Charles "Chuck" A. Miller III rellim@tulane.edu
Associate Professor of Environmental Health Sciences
374 Johnston Building, SL29
Tulane Univ. School of Public Health and Tropical Medicine
1430 Tulane Avenue New Orleans, LA 70112 (504)585-6942
Bionet.toxicology news group http://www.bio.net/hypermail/toxicol/current
[ NutraSweet, Equal, Canderel, Benevia, E951 ]
http://groups.yahoo.com/group/aspartameNM/message/927
Donald Rumsfeld, 1977 head of Searle Corp., got aspartame FDA approval:
Turner: Murray 2002.12.23 rmforall
A very detailed, highly credible account of the dubious approval process for
aspartame in July, 1981 is part of the just released two-hour documentary
"Sweet Misery, A Poisoned World: An Industry Case Study of a Food Supply
In Crisis" by Cori Brackett: cori@soundandfuryproductions.com
http://www.soundandfuryproductions.com/ 520-624-9710
2301 East Broadway, Suite 111 Tucson, AZ 85719
http://groups.yahoo.com/group/aspartame/messages
Aspartame Victims Support Group Edward Bryant Holman, Chief Moderator
826 members, 17,766 posts in a public, searchable archive
http://www.presidiotex.com/aspartame/ bryanth@presidiotex.net
http://www.HolisticMed.com/aspartame mgold@holisticmed.com
Aspartame Toxicity Information Center Mark D. Gold also Co-Moderator
12 East Side Drive #2-18 Concord, NH 03301 603-225-2110
http://www.holisticmed.com/aspartame/abuse/methanol.html
"Scientific Abuse in Aspartame Research"
http://groups.yahoo.com/group/aspartameNM/message/1131
genotoxicity of aspartame in human lymphocytes 2004.07.29 full plain text,
Rencuzogullari E et al, Cukurova University, Adana, Turkey 2004 Aug: Murray
2004.11.06 rmforall
"Schwartz ( 1999 ) also reported that methanol is converted to formaldehyde
which then accumulates in the cells.
Formaldehyde has been considered an inducer of cancer
and acts to alter DNA ( Ewertz, 1993; Ewertz and Gill, 1990 ).
Olney et al. ( 1996 ) reviewed and explained that ASP had mutagenic
potential.....
In this study, we found that, ASP did appear to have genotoxic potential
consistent with potential carcinogenicity.
According to these results, phenyalanine and methanol, which are metabolic
products of ASP, have a genotoxic risk for humans.
In contrast, ASP was not found as a mutagen in in vivo studies.
However, in the present study, ASP induced CA and micronuclei in human
lyphocytes dose-dependently.
ASP did not change the osmolality of the medium at the maximum
concentrations ( 346 milliosmol) when compared with untreated medium (342
milliosmol ).
It was reported that a deviation from physiological osmolality
( approximately 300 milliosmol ) can lead to genotoxic effects
( Nowak, 1984, 1997; Seeberg et al., 1989 ).
According to these results, we can conclude that ASP induced CA and
percentage of micronuclei by itself because it did not alter the pH and
osmolality of the medium.
As shown, there are several contradictory studies about genotoxicity and
carcinogenicity of ASP.
However, it must be taken into account that ASP induced the CA and
micronuclei formation in a dose-dependent manner.
It is not possible to conclude that ASP is safe according to these results.
Therefore, it is necessary to be careful when using it in food and beverages
as a sweetener."
Genotoxicity of aspartame 2004.07.29 plain text, Rencuzogullari E et al,
Cukurova University, Adana, Turkey 2004 Aug
Drug Chem Toxicol. 2004 Aug; 27(3): 257-68.
Genotoxicity of aspartame. reyyup@mail.cu.edu.tr
Rencuzogullari E, Tuylu BA, Topaktas M, Ila HB, Kayraldiz A, Arslan M, Diler
SB. Biology Department, Faculty of Arts and Sciences, Natural and Applied
Sciences Institute, Cukurova University, Adana, Turkey.
Poor memory is one of the main early complaints of aspartame reactors, who
are often people who use over 6 cans ( 2 L) diet soda daily for years.
The 12 experimental rats in this recent economical, focused study by
McConnaughey M et al (2004 May), drank a comparable level for 4 months,
about 13% of a 30-month lifespan. It is an excellent introduction to the
main issues.
Only after 3 months did the 12 aspartame rats show almost a doubling of time
to run a single-choice maze.
At 4 months, there was almost another doubling of delay: "...two of the
treated rats even went to the wrong side of the T-maze, totally forgetting
where the reward was." These are very powerful, worrisome results.
There were highly significant, neurologically relevant changes in certain
brain receptor densities, and changes in brain chemistry.
With 70 citations, the relevant scientific literature is well summarized.
Many other studies, often industry funded, often used single doses or
too short durations of exposure, along with lower doses, thus rarely proving
memory deficits.
The funding source for this extremely valuable study is not given.
It used a team of talented high school students.
The fact that certain brain receptor densitities increased, and that memory
deficit increase took 3 months to be significant, may reflect the paradox of
hormesis, the complex ability of organisms to make themselves stronger in
response to low levels of toxins:
http://groups.yahoo.com/group/aspartameNM/message/1055
hormesis: possible benefits of low-level aspartame (methanol, formaldehyde)
use: Calabrese: Soffritti: Murray 2004.03.11 rmforall
The most toxic part of the fragile aspartame molecule is its 11% methanol
component.
It is an open secret, admitted in a number of published studies for three
decades, that methanol is converted within hours by the liver into
formaldehyde and formic acid, both potent, cumulative toxins that affect all
cell types.
Few know that the classic "morning after" hangover from dark wines and
liquors is largely due to formaldehyde and formic acid from methanol
contamination, not the ethanol itself.
The actual disposition of these toxins in the tissues of human aspartame
reactors has never been determined, or, if determined, never publicly
published.
The study should be replicated, using methanol, formaldehyde, and formic
acid to verify if the same results obtain.
If blood and tissue samples have been stored, then the fast, cheap,
automated, highly sensitive Comet assay, often used to prove DNA damage from
formaldehyde, can be used to replicate the results by Yu F. Sakaki (2002),
whose intripid and much published team in Japan has found DNA damage,
testing 8 tissues from single non-lethal doses of aspartame
(near-significant high levels of DNA damage in 5 tissues) and 38 other
additives in groups of just 4 mice:
http://groups.yahoo.com/group/aspartameNM/message/935
Comet assay finds DNA damage from sucralose, cyclamate, saccharin in
mice: Sasaki YF & Tsuda S Aug 2002: Murray 2003.01.01 rmforall
[ Also borderline evidence, in this pilot study of 39 food additives,
using test groups of 4 mice, for DNA damage from for stomach, colon,
liver, bladder, and lung 3 hr after oral dose of 2000 mg/kg aspartame--
a very high dose. Methanol is the only component of aspartame that can lead
to DNA damage. ]
http://groups.yahoo.com/group/aspartameNM/message/1088
Murray, full plain text & critique:
chronic aspartame in rats affects memory, brain cholinergic receptors, and
brain chemistry, Christian B, McConnaughey M et al, 2004 May:
2004.06.05 rmforall
Pharmacol Biochem Behav. 2004 May; 78(1): 121-7.
Chronic aspartame affects T-maze performance, brain cholinergic receptors
and Na(+),K(+)-ATPase in rats.
Christian B, McConnaughey K, Bethea E, Brantley S, Coffey A, Hammond L,
Harrell S, Metcalf K, Muehlenbein D, Spruill W, Brinson L,
McConnaughey M. Department of Pharmacology, Brody School of Medicine, East
Carolina University, Greenville, NC 27858, USA;
North Carolina School of Science and Mathematics, Durham, NC 27811.
http://www.ecu.edu/pharmacology/faculty/mcconnaughey.html
Mona M. McConnaughey, Ph.D. Research Assistant Professor
Department: PHARMACOLOGY & TOXICOLOGY
Office: Brody Medical Science 6E-120A 252-744-2756
MCCONNAUGHEYM@mail.ecu.edu
This study demonstrated that chronic aspartame consumption in rats can lead
to altered T-maze performance and increased muscarinic cholinergic receptor
densities in certain brain regions.
Control and treated rats were trained in a T-maze to a particular side and
then periodically tested to see how well they retained the learned response.
Rats that had received aspartame (250 mg/kg/day) in the drinking water for 3
or 4 months showed a significant increase in time to reach the reward in the
T-maze, suggesting a possible effect on memory due to the artificial
sweetener. Using [(3)H]quinuclidinyl benzilate (QNB) (1 nM) to label
muscarinic cholinergic receptors and atropine (10(-6) M) to determine
nonspecific binding in whole-brain preparations,
[ the 12 ] aspartame-treated rats showed a 31% increase in receptor numbers
when compared to controls.
In aspartame-treated rats, there was a significant increase in muscarinic
receptor densities in the frontal cortex, midcortex, posterior cortex,
hippocampus, hypothalamus and cerebellum of 80%, 60%, 61%, 65%,
66% and 60%, respectively.
The midbrain was the only area where preparations from aspartame-treated
rats showed a significant increase in Na(+),K(+)-ATPase activity.
It can be concluded from these data that long-term consumption of aspartame
can affect T-maze performance in rats and alter receptor densities or
enzymes in brain. PMID: 15159141
http://groups.yahoo.com/group/aspartameNM/message/1067
eyelid contact dermatitis by formaldehyde from aspartame, AM Hill & DV
Belsito, Nov 2003: Murray 2004.03.30 rmforall [ 150 KB ]
"A 60-year-old Caucasian woman presented with a 6-month history of eyelid
dermatitis...
By strictly avoiding formaldehyde and all formaldehyde releasers for the
next 3 weeks, she improved only slightly.
Her problem, however, was subsequently solved when a local pharmacist
advised her to avoid aspartame.
She had begun using an aspartame-based artificial sweetener 5 months prior
to the onset of her dermatitis. [ 12 months of low-level aspartame use until
stopping. ]
Within 1 week of discontinuing the aspartame, her eyelid dermatitis resolved
completely and has not recurred over 18 months without specific
treatment....
Our patient was consuming an average of 80 mg (1.13 mg/kg) of aspartame
daily, well below the levels previously studied."
[ A packet of tabletop sweetener gives 37 mg aspartame, while a 12 oz diet
soda gives 200 mg aspartame. An aspartame reactor can have immediate strong
symtoms from an under-the-tongue wafer with 4 mg aspartame. ]
http://groups.yahoo.com/group/aspartameNM/message/1039
three-page review: aspartame (methanol, formaldehyde) toxicity:
Murray 2003.11.22 rmforall
http://groups.yahoo.com/group/aspartameNM/message/1026
brief aspartame review: formaldehyde toxicity: Murray 2003.09.11 rmforall
http://groups.yahoo.com/group/aspartameNM/message/1025
aspartame & formaldehyde toxicity: Murray 2003.09.09 rmforall
http://groups.yahoo.com/group/aspartameNM/message/1094
the 11% methanol component of aspartame becomes formaldehyde, now ruled a
carcinogen by WHO International Agency for Research on Cancer: Murray
2004.06.16 rmforall
http://groups.yahoo.com/group/aspartameNM/message/1084
26 stevia safety abstracts since 1993: aspartame vs stevia debate on
alt.support.diabetes, George Schmidt, OD: Murray 2004.05.25 rmforall
http://groups.yahoo.com/group/aspartameNM/message/1133
Mark Gold, most recent of 14 Rapid Responses to Aspartame
and its effects on health, BMJ: Murray 2004.11.06 rmforall
http://groups.yahoo.com/group/aspartameNM/message/1124
8 more Rapid Responses to Aspartame and its effects on health, BMJ:
Murray 2004.10.18 rmforall
http://groups.yahoo.com/group/aspartameNM/message/1120
5 critical Rapid Responses to Aspartame and its effects on health, Michael E
J Lean and Catherine R Hankey,
BMJ 2004; 329: 755-756: Murray 2004.10.05 rmforall
http://groups.yahoo.com/group/aspartameNM/message/1117
Aspartame and its effects on health, Michael E.J. Lean, Catherine R. Hankey,
Glasgow UK, British Medical Journal: 11% methanol component of aspartame,
and same level of methanol in dark wines and liquors, turns to formaldehyde
and formic acid, the main cause of chronic hangover symptoms: Murray
2004.10.04 rmforall
http://bmj.bmjjournals.com/cgi/eletters/329/7469/755#76712
***************************************************************
groups.yahoo.com/group/aspartameNM/messages
|


